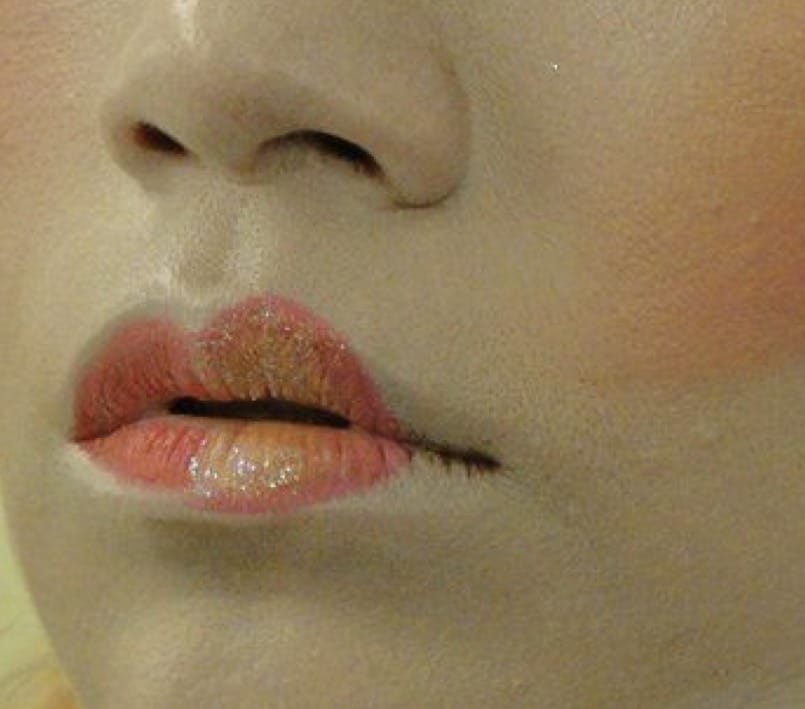To think that when Dr. Randal Haworth started his practice over 30 years ago, he was one of only a handful of leading plastic surgeons who specialized in lip reshaping surgery. Now, as one of the world’s most renowned lip lift experts, he has witnessed how upper lip lifts have exploded in popularity thanks to the influence of social media on the young and old alike. However, as with any trend, unintended consequences may arise such as the “neonatal deformity,” which originates from the congenital Apostrophe Lip. I first described this latter labial morphology in a chapter I authored for “Aesthetic Surgery of the Facial Skeleton”, a textbook edited by Dr. Steven Baker in 2019.
What Is an Apostrophe Lip?
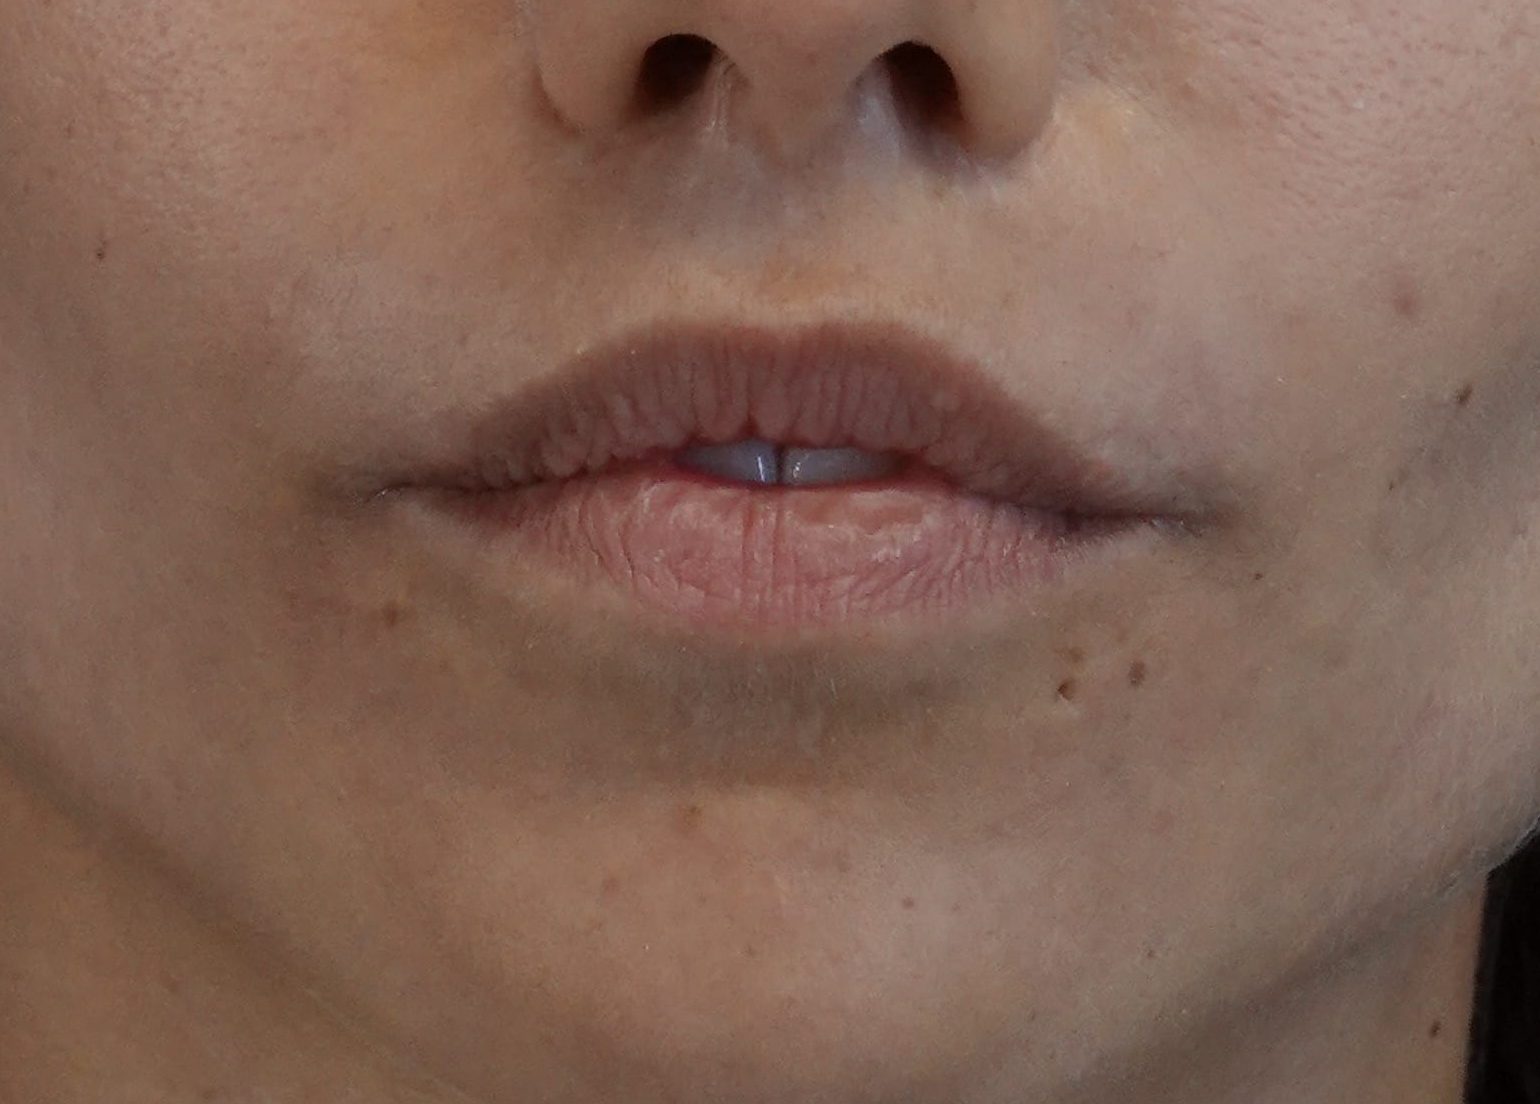
You might not recognize the name, but you’ve likely seen the effect: the pink vermilion (the visible part of the lip) is full and prominent only in the center, while the outer thirds taper off or even disappear. This narrowing gives the mouth a stylized, doll-like appearance reminiscent of Kabuki makeup, where the lips are intentionally painted small and central.
While deliberate in performance art, this effect is aesthetically unflattering when unintentional—and unfortunately, upper lip lifts performed without addressing corner anatomy often exaggerate this deformity.
Kabuki-style makeup mimicking an Apostrophe lip — note the abrupt loss of vermilion toward the corners, creating a slit-like mouth.
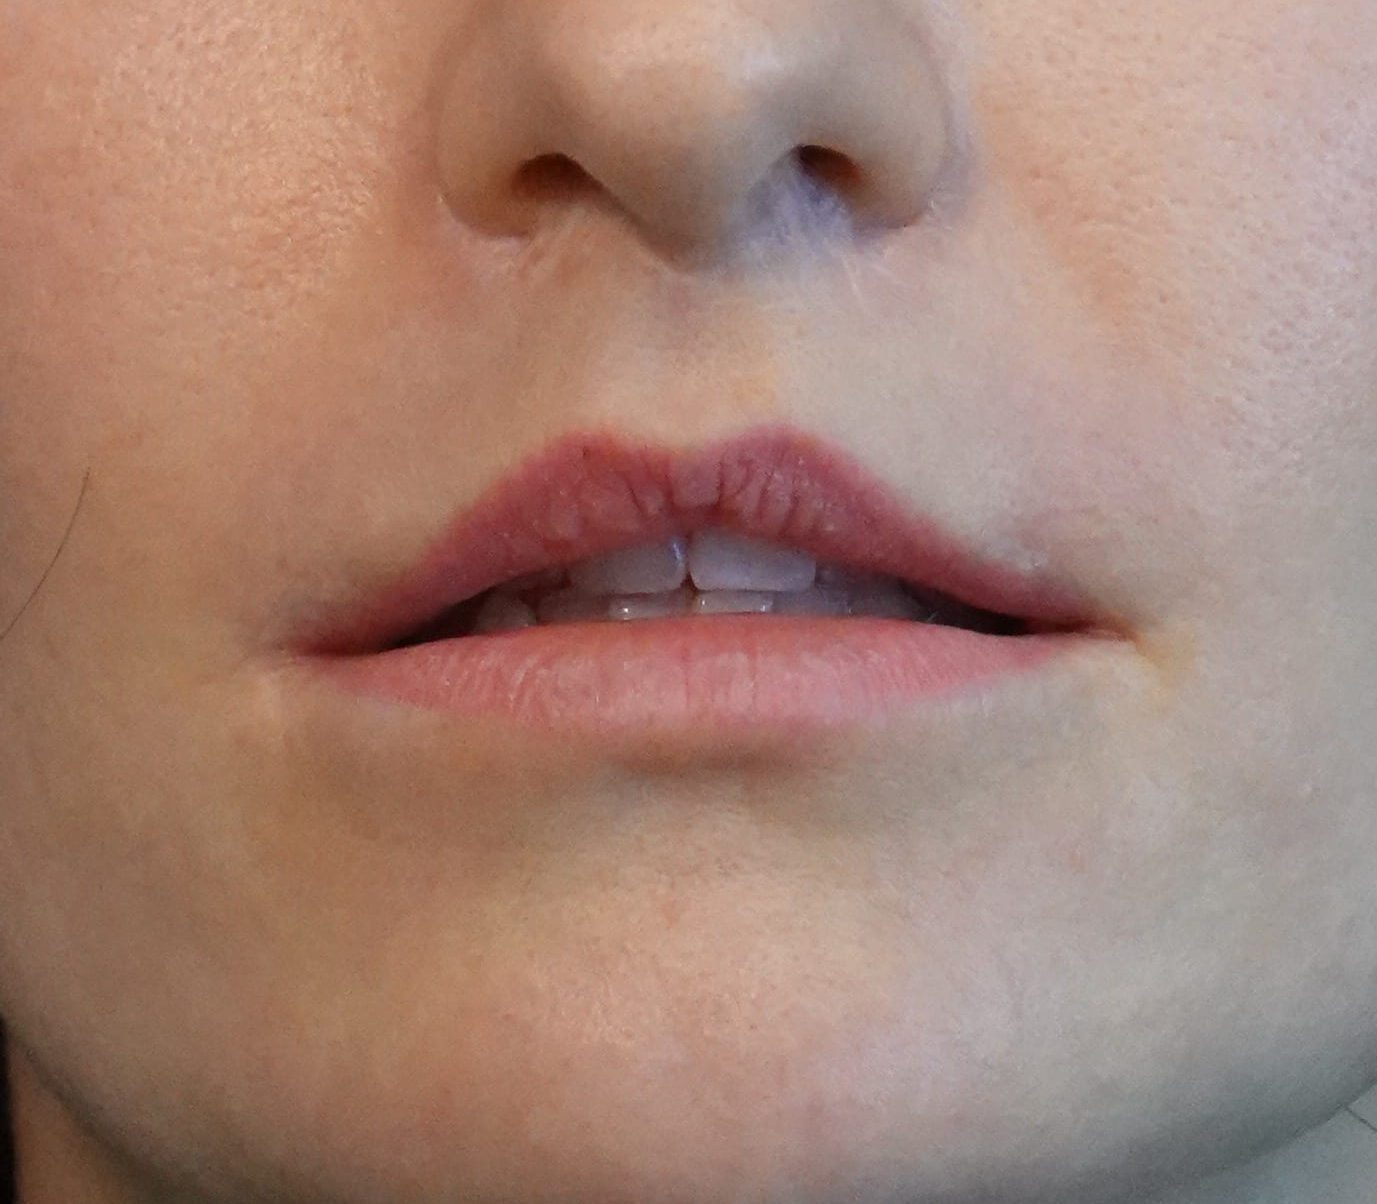
Another example of a stylized Kabuki “rosebud” mouth, often unintentionally replicated by improper upper lip lifts.
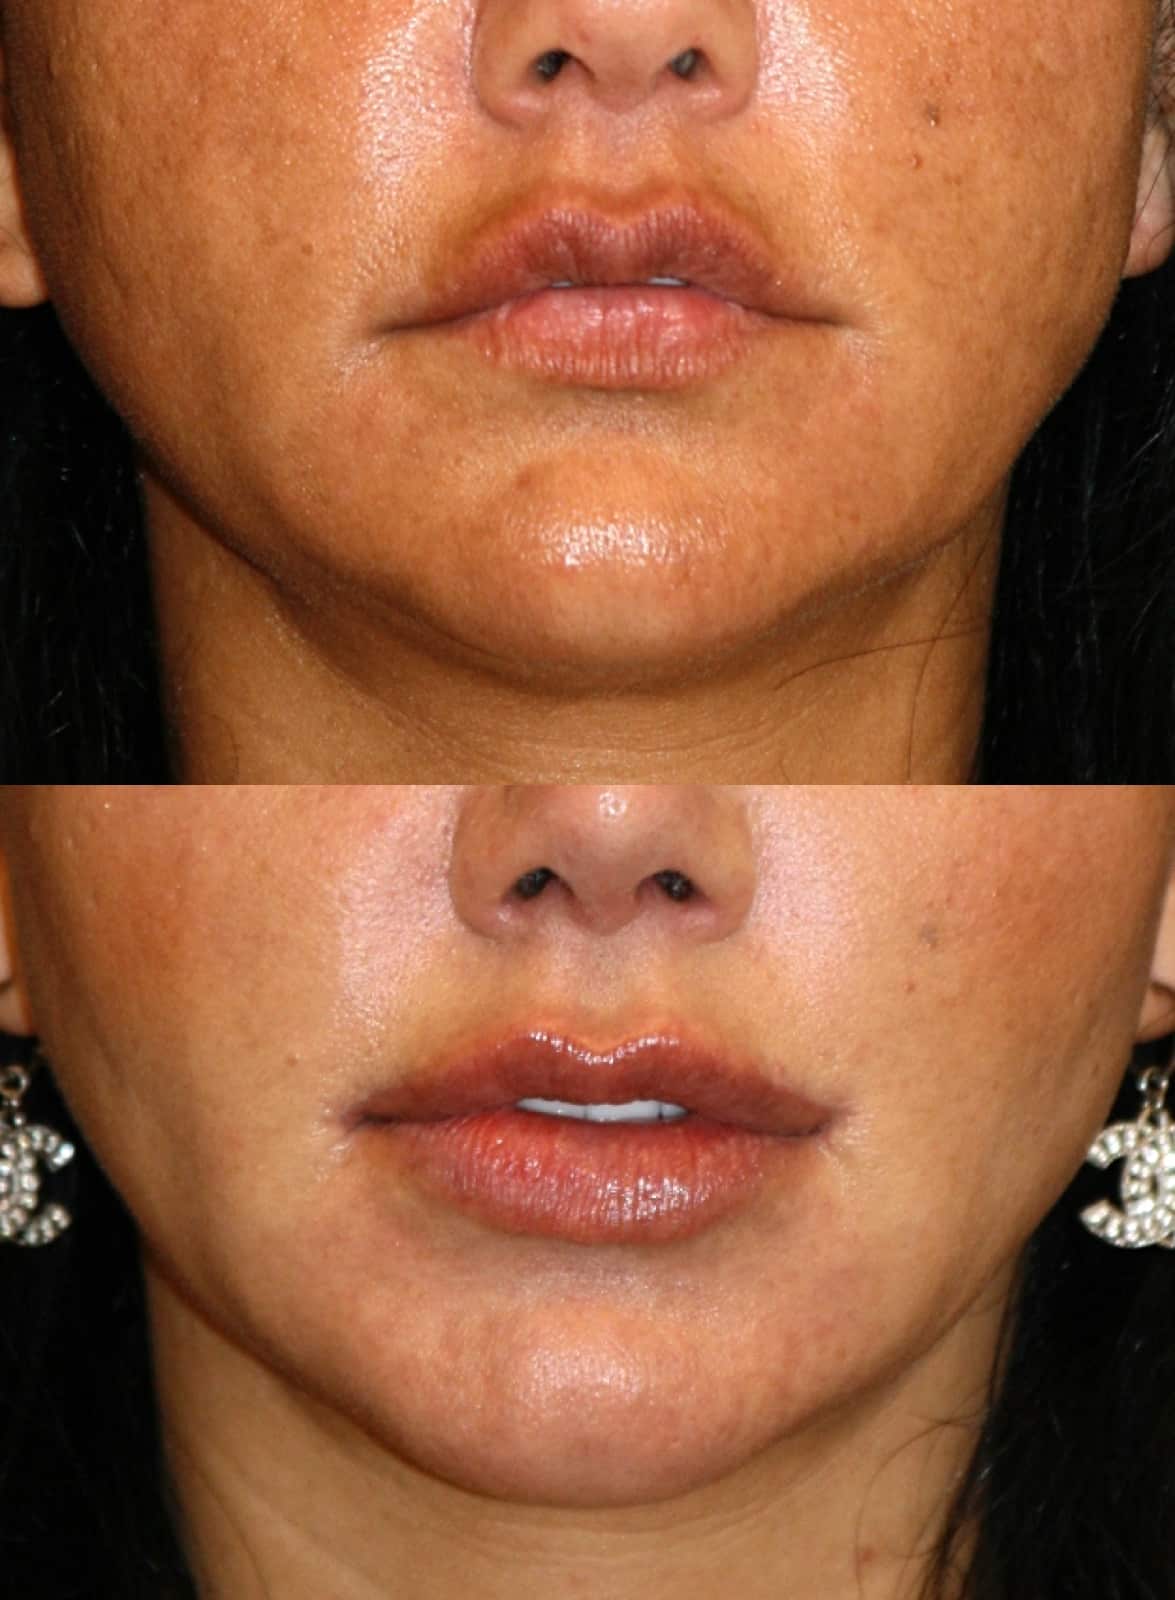
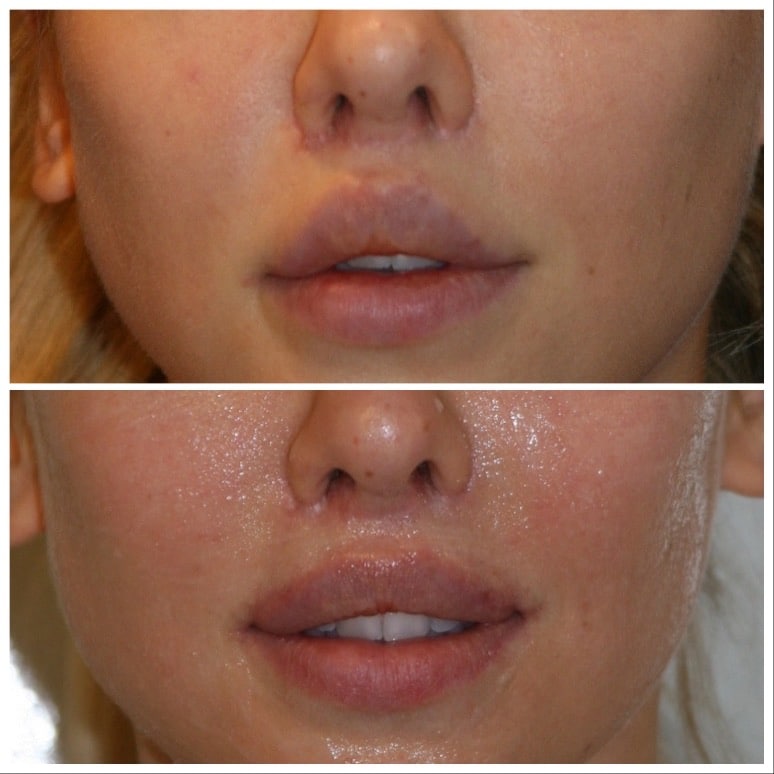
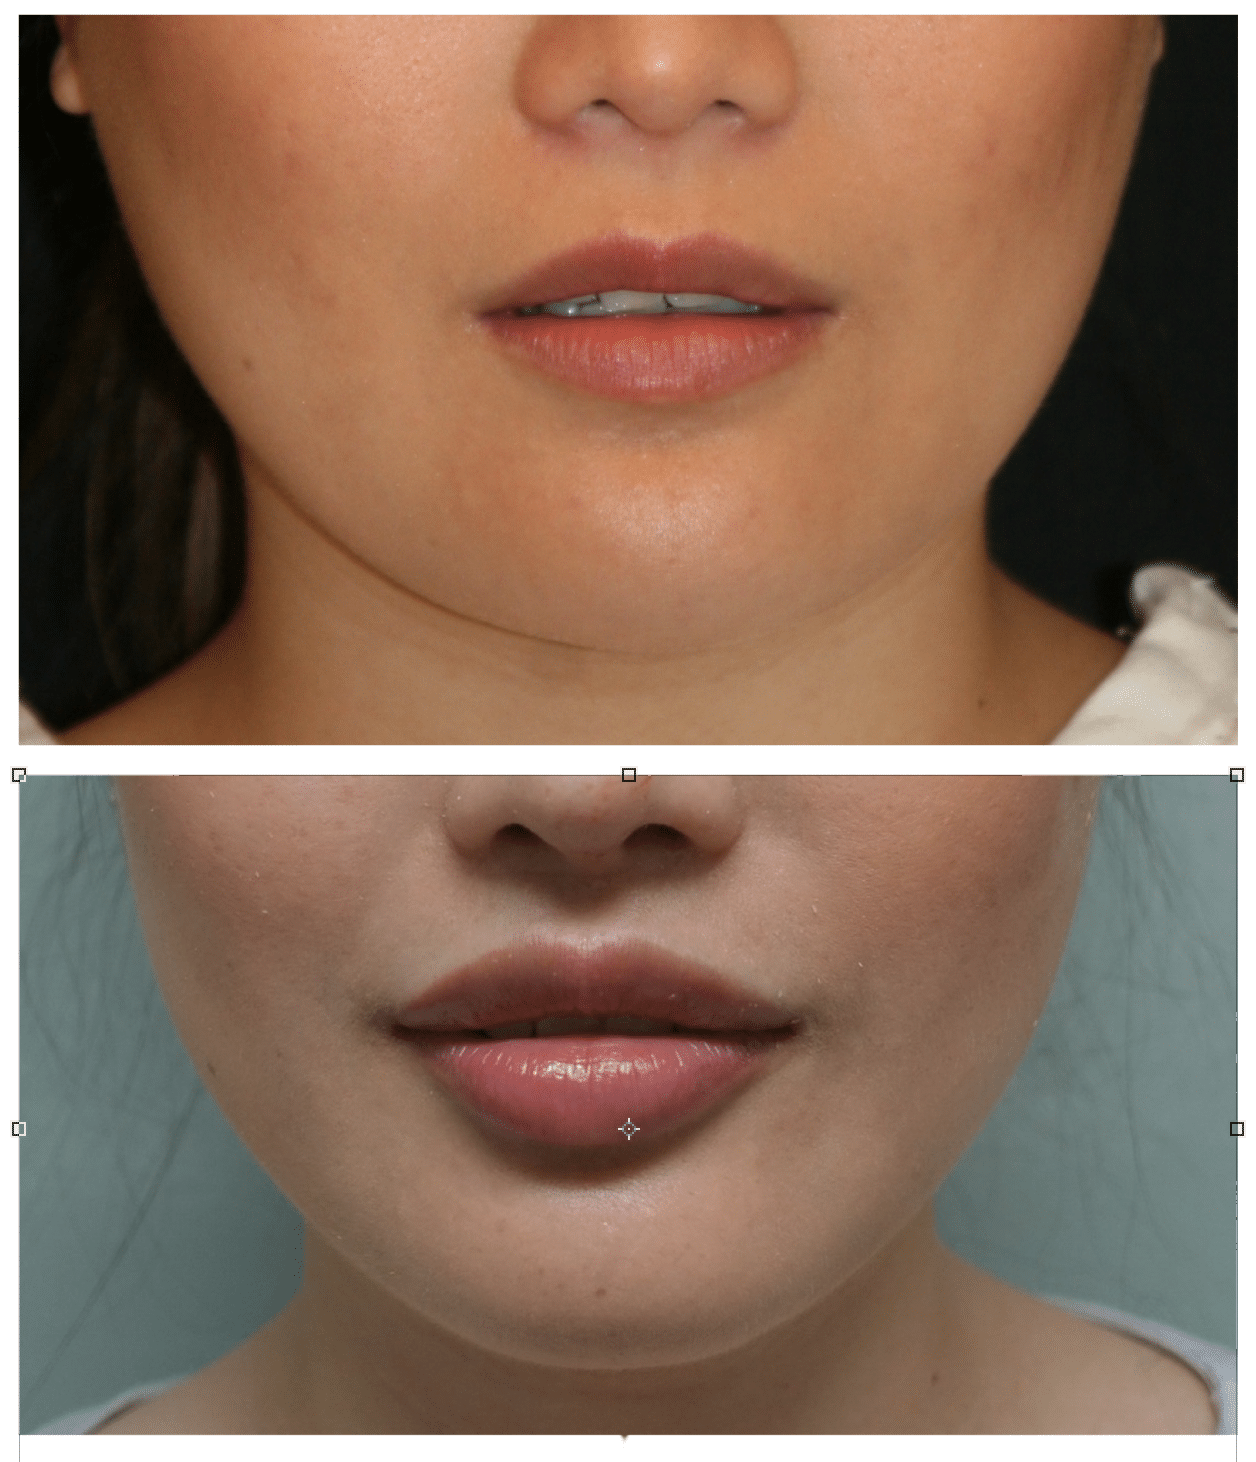
Before and after correction of an apostrophe lip using a medialized corner lip lift. This patient had chronic filler injections that exacerbated the deformity, narrowing the vermilion into a slit-like central zone.
How an Upper Lip Lift Can Create A Neonatal Lip
The neonatal deformity gets its name from the naturally recessed corners and centralized vermilion seen in newborns—charming in infants, but unflattering in adults.
Regardless of type, if an upper lip lift is performed without taking into account the oral commissures and lateral upper vermilion, a preexisting apostrophe lip can be exacerbated. The slope from the Cupid’s bow to the oral commissure (mouth corners) becomes unnaturally steep. The outer pink vermilion rolls inward or disappears entirely, leading to a pinched, slit-like appearance akin to that of a newborn. In essence, a neonatal deformity. Patients from around the world have come to me distressed by this outcome, often feeling disfigured and despondent.
Classic Neonatal lip deformity after an upper lip lift without regards to the oral commissures A moderate neonatal lip deformity after an upper lip lift and an inadequate traditional corner lip lift
The Medialized Corner Lip Lift: A Powerful Solution
Enter the medialized corner lip lift—a precise, elegant surgical solution I’ve refined over the years to correct these issues. It not only repositions the corners of the mouth upward but also:
Restores lost vermilion by rolling it outward, eliminating that paradoxically tightlipped “rosebud” look.
Corrects asymmetry, which is present in the majority of mouths.
Improves the marionette folds (those stubborn lines running from the corners of the mouth downward) that facelifts often miss.
Softens the harsh slope from Cupid’s bow to oral commissure, restoring a balanced, natural curvature.
This is a high-precision procedure involving design and execution tolerances as fine as a quarter millimeter. But when done correctly, the results are not only restorative—they are transformative.
This patient required a direct revision of her previous upper lip lift to correct pleating at the nasal base and a medialized corner lip lift to correct the neonatal deformity. A lower V–Y plasty was also performed.Another case of asymmetrical neonatal lip deformity after having undergone a previous upper lip lift simultaneous with a rhinoplasty. Dr. Randal Haworth corrected this with a medialized corner lip lift along with medical dermabrasion of her upper lip lift and nasal base/past rhinoplasty scars.. The vermilion was central and collapsed at the corners.
Final Thoughts
If you’ve undergone an upper lip lift and are unhappy with the corner distortion or feel like your lip looks smaller or more “pursed” than before—know that you’re not alone. These issues are more common than many realize, but they are entirely correctable.
Performed under local anesthesia, the medialized corner lip lift offers a sophisticated solution to restore harmony and confidence to your face.
The participants of “Married at First Sight Australia” all have one thing in common-lips preposterously out of proportion with their face. Like a loud out-of-tune instrument in an otherwise beautiful orchestra, these overinflated lips resemble baboon bottoms in heat and do no one any favours.
The characteristic overinflated lips so commonly seen nowadays in the social media age
The mistake made by the many so-called practitioners of aesthetic medicine, is to allow their own aesthetic judgment to be hijacked by the social media influencers. This encourages tunnel vision in doctors and nurse injectors alike, focusing only on lip volume and not on shape. Instead of enhancing facial sensuality, overly plumped lips tend to do the opposite and even age the face in a strange way. For example, the exaggerated lips of Jessika Power only serve to distract from her natural beauty while the lips of Martha Kalfatidis just draw attention to her other churlish facial plastic surgery including her rhinoplasty.
THIS IS A CLASSIC CASE WHERE THE INMATES RUN THE ASYLUM
As a renowned lip reshaping expert, I can say it is not just the lips but also the surgically and “filter enhanced” faces and bodies that send a bad message to young people. It breeds insecurity, narcissism, depression and bland conformity whereby everyone starts to look the same.
Stress, weather, chemicals and injury to the lip can all awaken the virus in your body. But needle punctures can be particularly triggering for cold sores. As one of the Beverly Hills top lip injector of fillers, Plastic Surgeon Dr Randal Haworth does see the occasional cold sore erupt 1-2 days after a treatment. It is for that reason, Dr Haworth recommends antiviral prophylaxis is select cases.
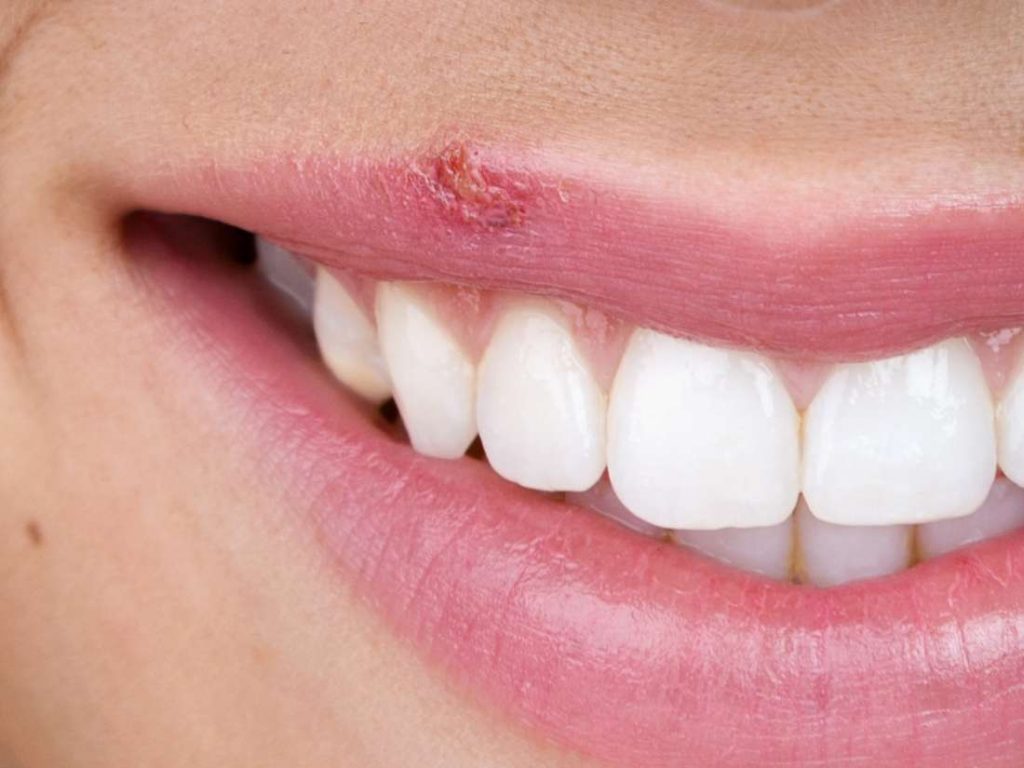
Cold sore herpes Simplex Type I which can occur after any lip procedure.
Of course, you can be prone to cold sores, get a lip filler and have no sign of an outbreak. But it’s good practice to be precautious and minimize the risk.
Dr Haworth notes that any cosmetic procedure which causes stress to your skin has the potential to stimulate cold sore recurrence. Cold sores are a prevalent affliction and are generally due to herpes virus (HSV) type one particular (generally oral herpes), with the minority (10%) being due to HSV type 2 (usually genital).
Many main infections of HSV-1 are asymptomatic, while recurrent infections can present as fever blisters at the vermillion border. Although cold sores may well not cause any long-term skin damage, they do possess the potential to cause scarring at the contaminated area.
Roughly two-thirds of a global population under 55 are infected with HSV-1. Primary illness develops in childhood through non-sexual contact usually, for example by sharing utensils or towels, but it is regularly assumed to be solely caused by kissing. If symptoms do present with primary infection, they take place two to 20 days after direct exposure.
Aesthetic procedures such as for example lasers, injectables, microneedling and chemical peeling often require limited or deliberate, manipulated trauma to skin, which includes the potential to trigger cold sore recurrence. Dr Haworth, the world’s foremost lip reshaping expert (including upper lip and corner lip lifts) will even warn his patients that his signature lip enhancements can trigger a herpes simplex outbreak. When a fever blister shows up after an aesthetic treatment, it could be devastating for the individual due to distress, pain and potential skin damage of a cosmetically very sensitive area. You will find a particular likelihood of scarring after ablative types of procedures (lasers, peels).
Cold sore prophylaxis can be recommended in the subsequent circumstances:
-More than three spontaneous occurrences every yea -Previous eruption at any time, as a result of a procedure -Lip augmentation and HSV eruption regardless of date or time -Facial resurfacing procedures; anything that breaches skin carrier, and especially medium or deep peels, facial skin lasabrasion, microneedling and microdermabrasion
Immunocompromised patients
Prophylaxis Dr Haworth recommends includes predosing with Valtrex 500mg daily for 2 days to continue for 3 after the procedure. He’ll substitute 1000 mg daily in particularly susceptible individuals.
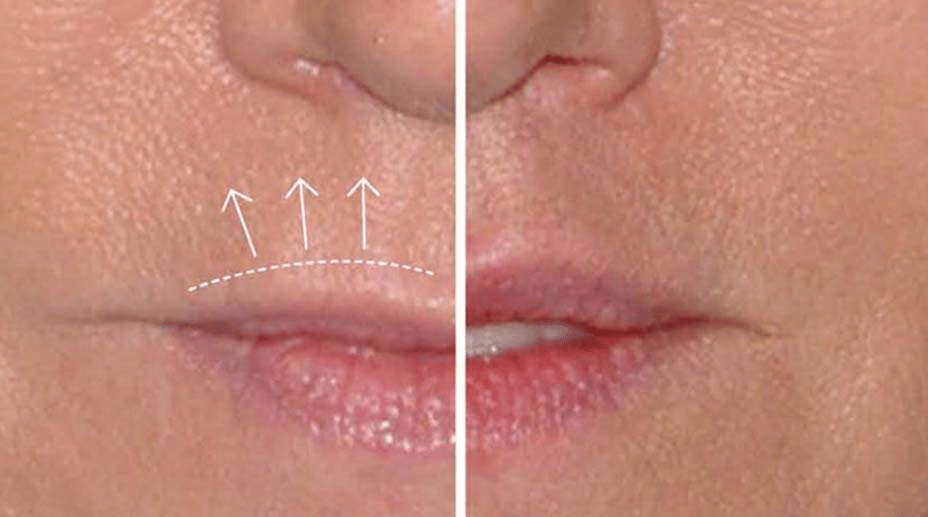
Blanketing Instagram may be the pout of the moment: an ample, upturned mouth revealing front pearly whites. It’s a look that has generated a fresh trend in cosmetic surgery: the lip lift. “Social media is driving a whole lot of esthetic selections,” says Andrew Jacono, a Park Avenue cosmetic surgeon, but “the voluptuous lip is not something you may get with injections. Filling lips only makes them appear to be sausages but doesn’t change their condition. Only the upper lip lift can naturally turnthe lip up and out.” The 30-minute office procedure excises tissue from just underneath the nose to shorten the distance between nose and mouth, causing the top lip to relax a bit, exposing more teeth, or “tooth show.” In Gen Z’ers and young millennials, it gives an ideal selfie pout; in older candidates, it can shave up to 7 years from the countenance ($3,000-$10,000).
As upper lips age, they elongate to eventually hide the upper teeth, while lower lips drop to expose the bottom teeth. Beverly Hills plastic surgeon Randal Haworth says lips, like breasts, go over time south. “When Angelina [Jolie] was 19, she had an insouciant mouth and had the Bardot upper tooth exposure ,” he says. “Nowadays her lip is starting to hide her teeth. It is the same with Jane Fonda.” Jacono offers that face-lifts improve the corners of the mouth but don’t address the problem: “Shortening the top lip is probably the most effective esthetic procedures I really do.”
Some surgeons will work with dentists to coordinate how much teeth to show.
“Showing 2 millimeters of tooth while you are at rest is ideal,says Manhattan esthetic dental professional Lana Rozenberg, who claims patients once requested heavier veneers to push away the lip for pout.
Now the Bugs Rabbit look can’t be avoided can be avoided, with surgeons just like NYC’s Oren Tepper working with esthetic dentist Jonathan Levine to open LipSync. “Ten years past, there was an ‘aha’ moment when hands were an era giveaway. Now we realize the mouth is a lot more telling, ” says Tepper.
A conservative upper lip lift result accompanying the Hollywood reporter article, performed by another plastic surgeon. result accompanying the Hollywood reporter article, performed by another plastic surgeon.
There is one disadvantage to a lip lift; its scar. “You can hide part of the incision inside the nostrils, but there is usually always some visibility at the bottom edge of the nasal area, ” says Beverly Hills cosmetic surgeon Leif Rogers, adding “If not done properly, it can change the look of the nose. “
Dr. Haworth acknowledged this as a problem about 15 years ago, ever since patients began complaining of this subtle nasal change. He realized there were two factors playing a part in this:
Excess tension around the incision line where the upper lip attaches to the nose and …
When the incision is made into the nose in a good faith attempt to hide the scar.
This led him to evolve his methods as a necessity to meet the increasingly discerning tastes of his patients. “Cutting into the nasal still can be a disaster even though it is motivated by goodwill towards the patients. By cutting into the nose, it breaks the circular stability of the nostril itself thus allowing it to “unfurl” and migrate inferiorly.
Another thing I have discovered is that when a lip lift is performed, it mustn’t just resist the downward forces of gravity but it must also resist the hundreds of thousands of mouth movements that occur per day. That’s why I needed to develop the OOS Upper Lip Lift which involves securing the upper lip to the strong lining of the bone around the base of the nose (periosteum). This technique is clearly superior to any skin-only lip lift whether it is modified or not. This results in a superior results in terms of beauty, scarring, lack of nasal distortion and longevity.
She recently confessed to spending $25,000 in a cosmetic surgery binge.
And Married At First Sight’s Jessika Power looked like a human Barbie doll in a video shared to Instagram on Tuesday night.
The 27-year-old flaunted her plump lips and hourglass figure in throwback footage from her recent NW magazine photo shoot.
Plastic fantastic! Married At First Sight’s Jessika Power looked like a human Barbie doll in a video shared to Instagram on Tuesday night
Posing in the makeup chair, the platinum blonde bombshell cast a sultry gaze at the camera before revealing her lacy white lingerie.
On Monday, Jessika confirmed she had spent $25,000 on a new set of veneers, two rounds of dental work, cheek and lip fillers, Botox and a brow lift.
After undergoing the cosmetic procedures in quick succession, she looks almost unrecognisable today compared to photos taken just a few years ago.
Showing off: Posing in the makeup chair, the platinum blonde bombshell cast a sultry gaze at the camera before revealing her lacy white lingerie
Transformed: On Monday, Jessika confirmed she had spent $25,000 on a new set of veneers, cheek and lip fillers, Botox and a brow lift. Pictured right: in April 2019, and left: in August 2017
She told NW magazine that relentless trolling about her appearance on MAFS left her feeling ‘shaken to the core’.
‘I’m a confident girl, but having thousands of people criticise me each day has shaken me to the core. I felt like I had heaps wrong with me afterwards,’ she said.
The Perth-born model added that she felt insecure about her looks partly because of the man she was previosuly dating: Daniel Webb.
‘I felt like I had heaps wrong with me’: Jessika told NW magazine that constant trolling about her appearance during MAFS made her feel ugly and insecure
‘Dan’s exes were all beautiful, including a Playboy bunny. I looked at pictures of her, then looked at myself and thought, “I look boring”,’ she confessed.
‘He would get Botox done on his forehead too and I felt I had to keep up with him.’
While Jessika is clearly pleased with her new look, not everybody is impressed.
My, how you’ve changed! Jessika was no stranger to cosmetic procedures before her debut on MAFS, having already undergone lip fillers. Pictured left: in 2017, and right: in 2018
Earlier this week, Beverly Hills-based plastic surgeon Dr. Randal Haworth said that Jessika’s excessively filled pout ‘resembles a baboon’s bottom in heat’.
‘Instead of enhancing facial sensuality, overly plumped lips tend to do the opposite and even age the face in a strange way,’ Dr. Haworth told Daily Mail Australia.
‘Jessika’s exaggerated lips only serve to distract from her natural beauty.’
She’s not finished yet! As for Jessika’s next procedures, she revealed that a non-surgical nose job and lipo-sculpture on her thighs and buttocks are next on the list. Pictured in April 2019
A renowned plastic surgeon has delivered a withering assessment of this year’s Married At First Sight stars, saying they are too dependent on fillers.
Beverly Hills-based Dr. Randal Haworth says the latest crop of brides have ‘over-inflated lips’ that sit uncomfortably with their faces and ‘don’t do them any favours’.
Speaking exclusively to Daily Mail Australia, the CEO of DrHaworth.com also claimed that reality TV stars more generally are sending a harmful message to young fans by excessively plumping up their features.
‘Their lips are preposterously out of proportion!’ MAFS brides Jessika Power and Ines Basic ‘are destroying their looks with facial fillers’, says a leading cosmetic surgeon. Pictured left: Jessika pre-2017, and right: in 2019
After being shown before-and-after photos of Jessika Power, Martha Kalifatidis and Ines Basic, Dr. Haworth didn’t hold back.
‘Like a loud out-of-tune instrument in an otherwise beautiful orchestra, these over-inflated lips resemble baboon bottoms in heat and do no one any favours,’ he said.
Speaking about reality stars generally, he said there is a risk they are projecting unrealistic beauty standards on to a young generation of women.
He added: ‘As a renowned lip reshaping expert, I can say it is not just the lips, but also the surgically and “filter enhanced” faces and bodies that send a bad message to young people. It breeds insecurity and bland conformity whereby everyone starts to look the same.’
‘These over-inflated lips resemble baboon bottoms in heat’: After being shown before-and-after photos of several Married At First Sight stars, Dr. Randal Haworth didn’t hold back. Pictured left: an undated photo of Martha Kalifatidis from several years ago, and right: in 2019
Several MAFS contestants, including single mother Susie Bradley, have admitted to using off-the-shelf lip fillers, such as Juvéderm.
In photos taken before their cosmetic transformations, the reality stars are almost unrecognisable compared to how they look today.
But Dr. Haworth believes that facial fillers have not necessarily improved or complemented the brides’ natural features.
‘Instead of enhancing facial sensuality, overly plumped lips tend to do the opposite and even age the face in a strange way,’ he observed.
Plump pouts: Several MAFS contestants, including Ines Basic, have admitted to regularly getting lip fillers. Pictured left: Ines in September 2018, and right: on April 18, 2019
‘The exaggerated lips of Jessika only serve to distract from her natural beauty’: Dr. Haworth told Daily Mail Australia that ‘overly plumped lips tend to age the face in a strange way’. Pictured: Jessika before and after having lip fillers
He added: ‘For example, the exaggerated lips of Jessika only serve to distract from her natural beauty, while the lips of Martha just draw attention to her other churlish facial plastic surgery, including her rhinoplasty.’
Dr. Haworth went on to say that ‘so-called practitioners’ of cosmetic enhancements are allowing ‘their own aesthetic judgment to be hijacked by social media influencers’ and reality stars like the Kardashians.
‘This [fixation] encourages tunnel vision in doctors and nurse injectors alike, focusing only on lip volume and not on shape,’ he said.
‘Doctors and nurse injectors alike focus only on lip volume and not on shape’: Dr. Haworth wasn’t a fan of Martha Kalifatidis’ cosmetic enhancements. Pictured before and after she underwent facial fillers
Speaking to NW magazine on Monday, Jessika confirmed she has spent $25,000 on her cosmetic transformation so far – and has no plans to slow down.
Last month, Ines also admitted she has been getting lip fillers ‘for years’.
Furthermore, Martha has acknowledged having Botox and facial fillers in addition to undergoing a rhinoplasty and breast enlargement.
Mummy makeover: Susie Bradley underwent extensive cosmetic work after having her first child. Pictured left: Susie in 2015, and right: earlier this year
When we choose to undergo a plastic surgical procedure, we do so to get a beautiful result which is balanced for the face and one that is as permanent as possible and one which doesn’t interfere with function.
I don’t think anyone would argue with the above.
Lips are a unique anatomical future. They connote youth, beauty and sexuality. However, their job is not only to look beautiful, they have to also function. This is contrast to a nose or an ear which have no moving parts.
And as a plastic surgeon helping to advance the field of lip reshaping surgery (LRS), this is where the challenge lays. When a patient asks me to make them a beautiful set of lips, I have to ensure:
a. A beautiful upper lip
b.A beautiful lower lip
c. Both upper and lower lips harmonize with each other
d.The harmonizing upper and lower lips harmonize with the surrounding face in terms of shape and scale (volume)
e.The upper and lower lips continue to harmonize well into the future (akin to a long-lasting result)
f. Scars are as imperceptible as they can be
g.The chance of nasal distortion and other complications are kept to a bare minimum
h.Lip function is retained (perhaps even improved with the new found confidence!)
i.Recovery is minimized whenever possible
j.A patient’s expectations are aligned with reality.
(Of course, “j.” should be at the top of the list. If a patient has unrealistic expectations, then no matter how successful a surgery is, if a patient in the end is dissatisfied, the surgery is a failure to them).
One of the cornerstones of lip reshaping surgery is the upper lip lift. Most of us appreciate that beauty is mostly conferred through shape and less so by colour and volume. The lips are no exception. An upper lip that is considered beautiful on a primal, instinctual level is one comprised of a short nose-to-lip distance, a beautiful “O” arch, a visible vermilion balanced with the size of the lower and, of course, an appropriate upper tooth exposure.
Sexy
After performing thousands of upper, corner and lower lip lifts, the secret to unparalleled longevity and a naturally beautiful lip shape is stability. One must understand that, like the hands, the lips move hundreds of thousands of times a day- eating, talking, expressing and other things that shall go unmentioned in this post. Therefore, for an upper lip lift to be successful in terms of beauty and longevity, it should not only resist the downward pull of gravity but also be stabilized against everyday movement (which contributes to re-stretching of the lip, obvious wide scarring and downward pull on the nose).
The OOS (Orbicularis Oris Suspension) superficial muscle technique provides this very stabilization by anchoring the superficial layer of Orbicularis Oris just below the dermis to the periosteum (or lining of the bone) below the nose. (The Orbicularis Oris is the circumferential, sphincter muscle that surrounds the oral aperture).
By stabilizing the lip in two directions bilaterally I am able to customize the curl and expression of the upper lip to make it not only youthful but sensual as well. The two direction approach is analogous to the way a marionette can come to life by the hands and strings which control it.
The skin-only lip lift is a far simpler operation to perform and solely involves removing skin and sewing the skin edge of the lip to that of the bottom of the nose. The only thing holding the skin-only lip lift in position are the dissolvable stitches in the dermis which are no match against constant daily mouth movement and gravity’s pull. As a result, there is a far greater likelihood of the nostrils being pulled downwards, obvious scarring, significantly decreased longevity and suboptimal aesthetics.
After a “modified “upper lip lift by another Beverly Hills Plastic surgeon, which is basically a skin-only lip lift marketed as something other than it really is. Note severe right nostril pulldown with bizarre pleat along with an “A frame” deformity and an exacerbation of her downward slanting can’t of her upper lips.
I can personally attest to the dramatically decreased longevity, unremarkable results, worse scarring and nasal distortion from the thousand or so skin-only lip lifts I performed in the 90s. Though the skin-only recovery is easier, the current version of the OOS upper lip lift may allow the patient to appreciate results as early as 10 days. Not only does the OOS technique shorten the distance between the nose and lip but it also allows upper tooth show( that goes without saying really), subtle added rollout of the upper lip’s pink vermilion, welcomed narrowing of the aperture of the mouth (that gets wider with age) and even noticeable reduction in the nasolabial folds. Contrary to some misperceptions, no muscle is removed and no cases of permanent numbness or any paralysis ever encountered.
After an OOS upper lip lift by Dr Haworth. Note minimal scar and no nostril descentAfter an OOS upper lip lift by Dr Haworth. Note minimal scar and no nostril descent
More and more people are realizing that the upper lip lift( and other LRS techniques) may play as important a role as a facelift and eyelid surgery in facial rejuvenation. Choosing proper techniques, performing them well and understanding how all elements of the lip work together can be the ultimate magic trick to transform a face from “Meh to Mwah”!
Dr Haworth
July 2018
Plastic surgeon Randal Haworth, MD, is taking the next step in his career with the launch of a stylish, comprehensive aesthetic care facility.
Randal Haworth, MD, made a name for himself in aesthetics in the early 2000s when he joined Fox television’s reality show, “The Swan.” On the program, he was part of a team of plastic surgeons, stylists and makeup artists who dramatically transformed participants’ appearances, Earlier this year, he transformed his own Beverly Hills, California-based practice when he moved to a new, custom-designed facility that incorporates a full range of aesthetic services—from facials and nutritional services to fillers, lasers and surgical procedures.
Dr. Haworth’s design philosophy for the new Haworth Institute was nature meets high-tech.
“It’s a beautiful place, and all our services are under one roof—the surgical center, my clinic and our new noninvasive center, Self Centered Aesthetics,” says Dr. Haworth. “Patients always asked us, ‘What else can you do?’ ‘How do I maintain this?’ It just doesn’t make sense nowadays not to offer the full-range of aesthetic treatments.”
In addition to laser treatments and injectables performed by Dr. Haworth and his R.N., celebrity esthetician John Tew performs signature facials and naturopathic doctor Matea Polisoto, who goes by “Dr. Matea,” offers IV therapy and nutrition counseling. “Like John, she has a very big following in Beverly Hills and beyond,” says Dr. Haworth. “She is involved with IV therapy, which helps augment the pre- and postoperative surgical experience, and optimizes healing.
“The people working with me are just as important as the surgeon—it’s all about having a team,” he says.
The Frustrated Artist
Born in Los Angeles and educated in England, Dr. Haworth has a somewhat unusual background for a Beverly Hills plastic surgeon. “My dad was English and spent World War Il in London selling bootleg whiskey during the Blitzkrieg. My mother and her family lived in Holland during the German occupation,” he says.
Following the war, both of his parents immigrated to the United States seeking opportunities, of which there were few in post-war Europe. “They met, and I was born in Los Angeles. But my dad always wanted me to be in England eventually,” says Dr. Haworth.
When he was 9 years old, he and his parents drove to Central America and boarded a cargo ship to England. During his school years in London, Dr. Haworth became enamored with the arts. “l always drew—and I was very good at a young age. In University I joined band. I was really into the arts, and that’s what I wanted to pursue,” he says. “But my parents, being war babies, wanted a doctor in the family and I was their only child.”
During a road trip prior to his final year at the university, he shared his goals with his parents. “We were in a VW bus and they said, ‘We’ll disown you if you become an artist. Make your decision’—it was really bizarre,” he says. His mind flashed back to a BBC interview of Kurt Wagner, MD, he had seen when he was 13. “l said, ‘Then I’ll be a plastic surgeon,’ having no idea what was involved in that.”
He came back to the U.S. and enrolled in medical school at the University of Southern California. Following graduation, he completed a five-year general surgery residency at Cornell Medical Center in New York. Dr. Haworth made his way back to the West coast for his plastic surgery residency at the University of California, Los Angeles.
“After my residency, I had no money so I was anxious to go into practice. I thought, well then I have to goto Beverly Hills because that’s where successful plastic surgeons go,” he says.
Another surgeon offered to rent him a space in his clinic’s kitchen, which was housed in one of the most desirable medical buildings in Beverly Hills. “He had a little pocket door in front of the kitchen so I stayed in there,” says Dr. Haworth. “During my clinic days, I would take his diplomas off the walls in the two little exam rooms and put mine up, and that’s how it started.
“l look back fondly on those days now, but it was horrible at the time. If I had two surgeries in a month, it was a great month.
Finding His Niche
During his UCLA residency, Dr. Haworth won a plastic surgery research prize for his lip surgeries, which provided a unique niche with which to build his practice, More than 20 years later, he has patients from all over the world who travel to the Haworth Institute for their lip surgeries.
“You can be the best doctor in the world, but if you don’t have marketing, no one will know about you,” he says. “So I leveraged that award and started getting known for lips, even though my favorite surgeries are noses, mid- facelifts and what I call hyperaesthetic surgeries where we change everything. The lips are what I was known for, and now I get jazzed by that because there’s really no competi- tion in the world for these surgeries.”
He offers upper, lower and corner lip lifting procedures as well fat transfer and F.A.T.M.A. (fat transfer & mucosal advancement). “l do many types of lip lifts because it is shape before volume; there are many things that fillers alone cannot do,” he says.
Embracing and Investigating New Technologies
Despite the limitations of traditional filling techniques, Dr. Haworth has embraced dermal fillers as effective tools to perfect his patients’ lips. In some cases the new, less invasive procedures are even surpassing what he can achieve in the O.R.
“Our mouths get wider as we age and our lower teeth become visible,” he says. “People will often just fill the lower lip horizontally, which won’t help with these concerns.”
In his surgical center, he performs lower lip V-Y plasty procedures to narrow the mouth, lift the bottom lip and pout out the middle third of the lower lip. But, due to the minimal improvement, he recently became interested in the idea of using vertical filler injections to lift and shape the lower lip.
“About three months ago, I started injecting vertically into the lower lip. I place my long cannula or a long needle vertically from the bottom of the prejowl sulcus all the way to where I see the needle blanching on the vermillion on the back of the lower lip on the sides. Then I inject vertically as I pull the needle out,” he says. “l am seeing such dramatic elevation of not just the lower lip but the whole corner of the mouth—the marionette folds are dramatically reduced and the labiomental sulcus opens up.”
He is calling this the Caisson technique after Caisson beams in construction. “The patients are three months out now, and the results are far better than what we see with the lower V-Y plasty in hiding the lower teeth,” he says.
Dr. Haworth is investigating new ways to augment and lift lips using dermal fillers.
“l love doing surgery, but plastic surgery is in some ways a dying field,” he continues. “The future of plastic surgery lies in the lab, not the operating room. Eventually they are going to know how to stop senescence. In the meantime, the future of aesthetics is laying more and more in lasers and newer, better fillers, and I want to stay on the forefront of that.”
His biggest challenge is determining which new technologies and procedures live up to the hype—and resisting the urge to bring in every new device about which patients inquire. “Sixty to seventy percent of all new medical cosmetic technologies overpromise and under deliver,” he says. “First it’s a big ‘Wow!’ Then results are ‘operator-dependent,’ then it’s gathering dust, so I vet all these technologies and only offer the ones I believe are proven to work.
“What I want to offer my patients with the Haworth Institute and Self Centered Aesthetics is more than one-stop aesthetics, It’s the tools and knowledge to deliver the absolute best treatments for their individual concerns and lifestyles,” continues Dr. Haworth. “We have a turbocharged armamentarium of proven noninvasive treatments to carry on the philosophy that I espouse in my surgeries, which is really detailed aesthetic work.”
As trifling as it may seem to the layperson, aesthetic surgery is serious business. Apart from obvious cosmetic ramifications, the seriousness becomes understandable when one considers that the surgeon must first make a healthy patient temporarily unwell in order to make he or she look better in the end. It is for this very reason plastic surgeons have an added unique responsibility which surgeons of other specialties simply do not bear. Choosing to undergo elective surgery is a series of decisions made by both the surgeon and the patient. As with all aspects of medicine, nothing is absolute, it is about controlling probability.
In this day and age, patients increasingly view plastic surgery as nothing more than a haircut with a short recovery, let alone one with a complication. Even under the best of hands, a complication can arise for any number of reasons and if it does, acting as a team with your surgeon is crucial. Whether following a facelift, rhinoplasty or any plastic surgery for that matter, almost all complications can be fixed in the end, even if multiple surgical revisions are needed.
It is normal for the layman to consider surgical results as either “good” or “bad”, but those adjectives can be misleading and are certainly inadequate in revealing the true story behind the result.
“Good” surgery with a complication is not the same as “bad” surgery per se. In other words, complications do not all come from “bad” surgeons and indeed, “bad” surgeons may have successfully completed an operation without encountering obvious complications. I think it fair to say most patients consider themselves as good people and if a complication happens to them, they will perceive themselves as victims of a bad surgery and by extension, a bad surgeon. So what is the difference between “bad” surgery and a “good” surgery with a complication?
Look at it this way… in any profession, there are the “good”, the “bad” and the “excellent”. For the sake of this discussion, let’s just oversimplify the comparison between “good” and the “bad”. Since plastic surgery is as much an art (or at least an artisanal craft) as it is a science, whereby results are measured both objectively and subjectively, it is not unreasonable to compare a plastic surgeon to any artist or craftsman, including sculptors, painters and woodworkers. Artists filter their talent and vision through years of experience to not only earn but continually solidify their reputation as either being “good” or “bad”. Moreover, good artists become respected by not just producing one “good” piece but doing so consistently, whereas the “bad” consistently create sub par results as judged by the median consensus.
However, all artists, whether good or bad, are limited by the quality of material with which they work. It is known that Michelangelo’s David has been deteriorating at a far more rapid pace than would be expected because of the poor quality of its marble composition. Bernini also broke a piece of marble in half through chiseling into an unexpected vein in the stone causing him to start all over with a brand-new block. Does that make him a bad artist? Hardly not.
In other words, complications happen and that’s why there are consents to protect not only the doctor but also the patient. Consents should ensure the patients are informed as to the shared risk both they and the surgeon take when undergoing surgery.
Many complications are avoidable. Both doctors and patients must do their part to optimize a certain outcome and minimize the risk of complications. Patients must avoid certain medications that may promote bleeding, cease all smoking for optimal circulation, follow instructions and take medications as prescribed. Otherwise, surgery may be self-sabotaged. On the other hand, surgeons must do their part in educating and performing the proper operation in the right patient with skill and dedication.
Other complications are unavoidable and just because they may be explainable in hindsight does not mean they were avoidable within the context they occurred. This is why it is paramount that patients disclose all of their medical history and follow their surgeon’s instructions to a T in order to minimize unexpected situations such as abnormal bleeding, poor wound healing, etc..
What spurred me to write this particular blog was a recent experience having performed a complex revision rhinoplasty on a dear friend of mine of 20 years. Unfortunately, this advanced detailed nasal reconstruction was exacerbated by unexpected physiological conditions including excessive bleeding and poor tissue characteristics. The next day, the patient presented with so much swelling underneath the pressure cast that it was being pushed off the face. The swelling was a hematoma which I immediately evacuated from under the skin (it was 4 1/2 mL, being the largest nasal hematoma encountered by either my colleagues or myself). Accompanying this was necrosis (death) of the columellar skin (the partition separating his left and right nostrils). This was particularly disappointing to say the least because the surgical results in terms of nasal shape, symmetry, tip definition and projection were otherwise excellent. Yet losing coverage over the columella would have serious ramifications.
Despite attempts to bring vascularized tissue using local intraoral flaps, my friend eventually needed the help of a certain specialist to bring fresh tissue to the columella below the nasal tip with a temporary forehead flap.
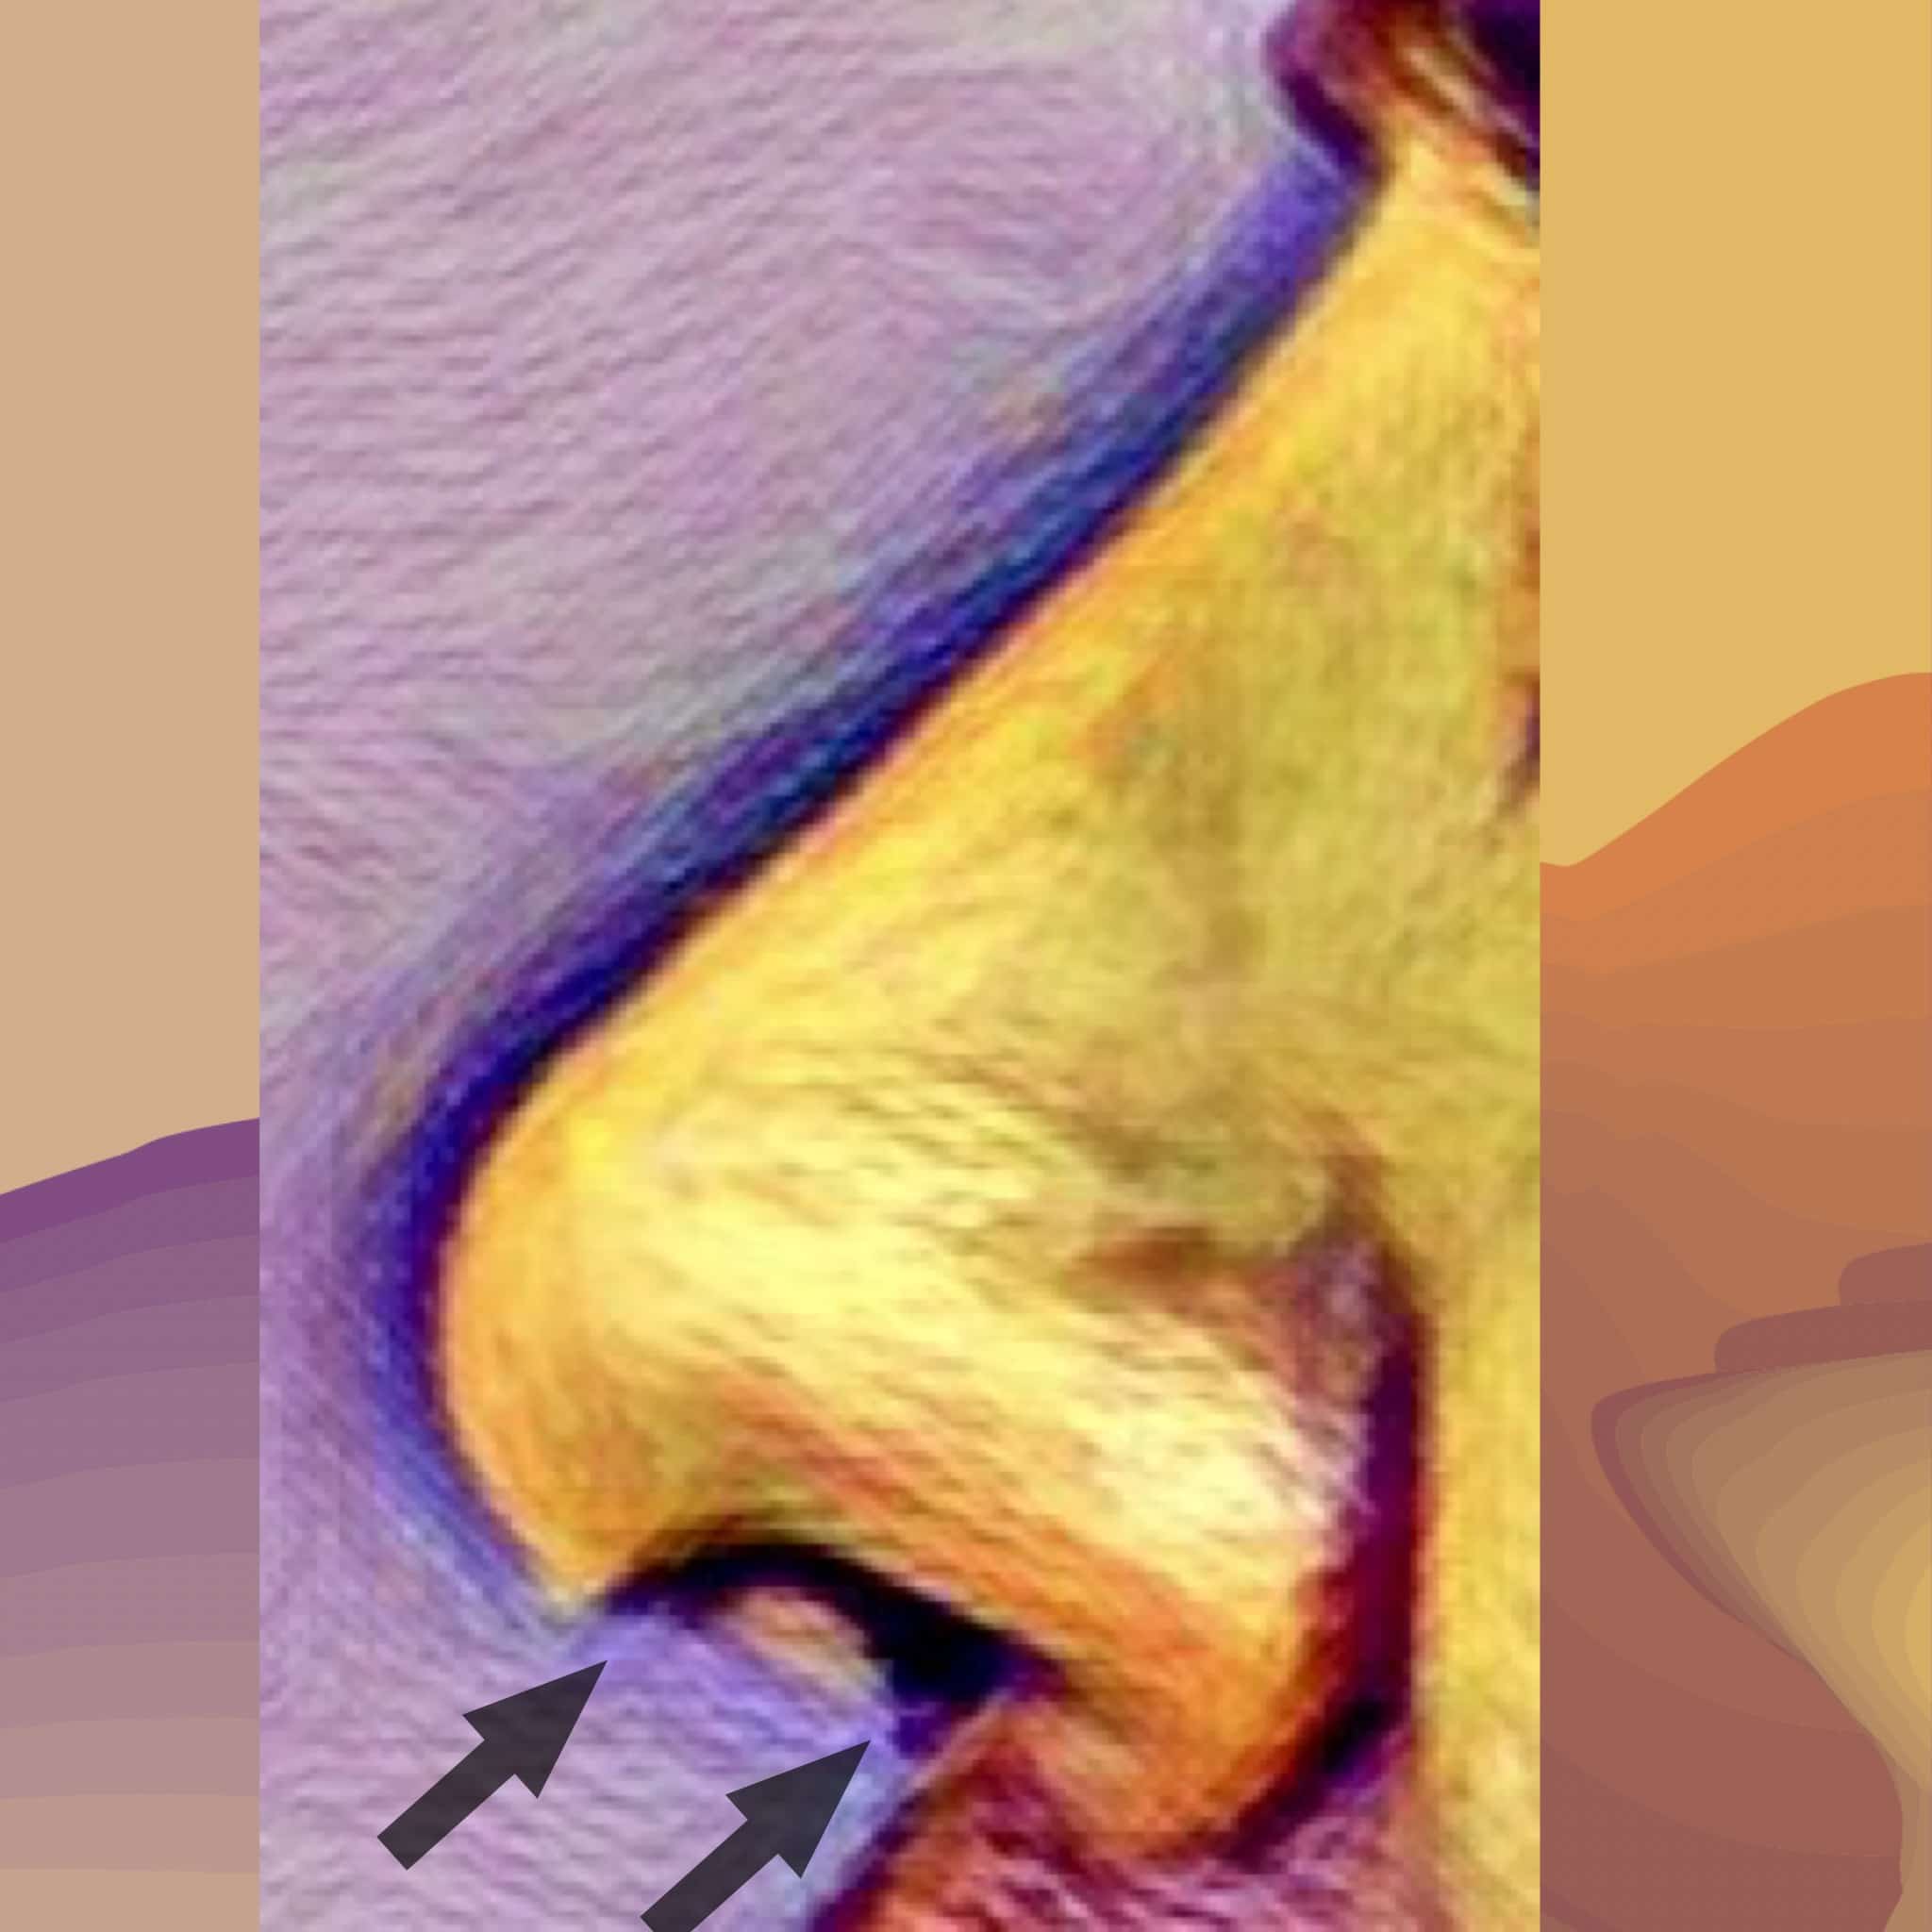
The arrows on the drawing illustrate that portion of the nasal skin (overlying the columella) that was necrotic. Replacement is required through vascularized tissue flaps
Albeit exceedingly rare, this 1.5 x 1.2 cm skin loss was enough to eradicate not only their trust in me as a surgeon but also our long term friendship. Most patients understandably experience a spectrum of emotions including panic, sadness, denial, anger and ultimately acceptance from a complication such as this. However, nothing could prepare me for the degree of ongoing vengeful anger and hostility the patient and their partner have directed towards me including threats to go to the press and ruin my reputation.
Anger is not only destructive but also lacks focus, therefore it can be especially counterproductive to both healing and a good result (not to mention friendship!). Premature castigations of blame fuel brash, illogical decisions which actually complicate the original complication.
Understanding the differences between “bad” and “good” surgery and “good” surgery with a complication can certainly help put things in perspective. When a patient concedes the net surgical aesthetic result, at least in terms of shape and symmetry, as good if not excellent, he or she is less likely to question, and more likely trust, their original choice of surgeon. Whether their breast lift incision opened or, as in this case, a small but strategic portion of nasal skin died, the affected patient will see the “bigger picture” and believe their surgeon will do the right thing by having their best interests at heart. This same patient understands that they were not necessarily a victim or unjustifiably punished by “bad” surgery. Instead, they will accept things for what they are, learn patience and develop a sense of optimism to set themselves up for the best possible outcome in the future.
The majority of complications concern wound healing and minor infections. For these, possible antibiotics and the “tincture of time” for healing to occur are required. Other times, simple, clinical interventions such as laser treatment, injections, the occasional scar revision and creams are all that are needed.
Other complications require more invasive solutions. Depending on the type of complication, an expeditious trip to the operatory maybe all that is required (e.g.,to drain a hematoma) whereas staged surgical revisions may be undertaken in the extremely rare case of tissue loss.
Most surgeons will recognize if a particular complication is beyond their level of expertise. A patient should not feel abandoned or simply passed off if they are referred to another expert if a complication warrants it. It is important to recognize that medicine is team work and the referral is simply a reflection of the original surgeon’s dedication to the best outcome possible.
Emotional advice after a complication
–Watch out for advice with an agenda. It is understandable that if a complication does arise, fear and anxiety will prompt you to seek solace and advice from friends and family members. While this is wholeheartedly encouraged, it is important to remember that not all the advice given is good especially considering that those giving advice are not often doctors nor do they know the intricate details of the patient’s particular case. Though most advice is well-meaning in intent, some may be motivated by guilt, jealousy, personality disorders or just plain ignorance. Furthermore, the advice a patient may obtain from elsewhere may be counterproductive because it may only increase their level of anxiety.
–Stay optimistic and avoid jumping to any pessimistic conclusions. It is not unheard of that acute anxiety will provoke a patient to impatiently reach for the help of an alternative plastic surgeon. Unfortunately, some plastic surgeons may be unscrupulous and advise the fragile, highly suggestible patient into unnecessary and ill-timed surgery claiming it is urgently needed to prevent some permanent deformity. Always keep a line of communication open with the original plastic surgeon to not only help allay personal fears but also be guided in the right direction with a second opinion if necessary.
After more than two decades of commitment to delivering the best of what plastic surgery can deliver in terms of aesthetic results and quality-of-life improvement, top Beverly Hills plastic surgeon, Randal Haworth, found it time to expand his philosophy into an adjacent arena. That arena is the nonsurgical approach to optimize the patient’s aesthetic wellness. Dr. Haworth has maintained that future advances in plastic surgery will not lie solely in the operatory but more in the laboratory. Specifically, advances in lasers, injectables, light and genomic therapy will take precedence over any evolutionary steps in surgical technique. Currently, non-surgical cosmetic procedures are rapidly evolving to meet the expectations, budgets and lifestyles of patients of all backgrounds and consequently, their popularity is exponentially increasing every year.
As a world-renowned expert in facial plastic surgery (including rhinoplasty, lip lifts, face lifts, eye lifts and even bodywork such as breast augmentation) Dr. Haworth has come to a point where he need not confine his artistry mainly to the syringe and scalpel but also safely and reliably imbue it into noninvasive aesthetic medicine. Consequently, he and his team at the Haworth Institute have founded Self-Centered Aesthetics, a center devoted to optimum physical appearance, through the safest, most reliable state-of-the-art technology.
Self-Centered Aesthetics (SLF-CA)will be catering to the vast majority of patients’ aesthetic needs.
Among the services SLF-CA will be offering are:
3. Removal of wrinkles, fine lines and sagging folds via a variety of methods including essentially all fillers, microneedling with PRP, Botox and lasers (Spectra®, Encore® Active and Deep FX™ fractionated CO2, ResurFX® fractionated erbium and IPL® Photofacial)
4. Treatment of brown spots, brown patches, red discolorations and spider veinsutilizing proven laser technology (IPL® Photofacial and Spectra®)
5. Tattoo removal(Spectra® and other lasers)
6. Noninvasive body fat reduction through SculpSure®, a laser designed to achieve up to 20% fat reduction in 25 minutes with virtually no discomfort and absolutely no incisions.
7. Facial feature improvementthrough the selective use of fillers and Botox®. With refined aesthetic sensibility and an astute artistic sensitivity, fillers (both temporary and permanent), can enhance all aspects of the face. However, to maximize the beauty of a result without artifice or outward fakery requires customized planning to balance patients’ needs with their individual expectations. From a flat forehead with hollow temples to sunken cheeks and dark eyelid circles to thin lips and an ill-defined jawline, the professionals at SLF-CA under the auspices of Dr. Haworth dedicate themselves to make you look your very best!
Additionally, our CENTER will offer aesthetician services to maintain and fine-tune your SELF and your AESTHETIC results.
Self-Centered Aesthetics™ will be coming soon. www.selfcenteredaesthetics.com