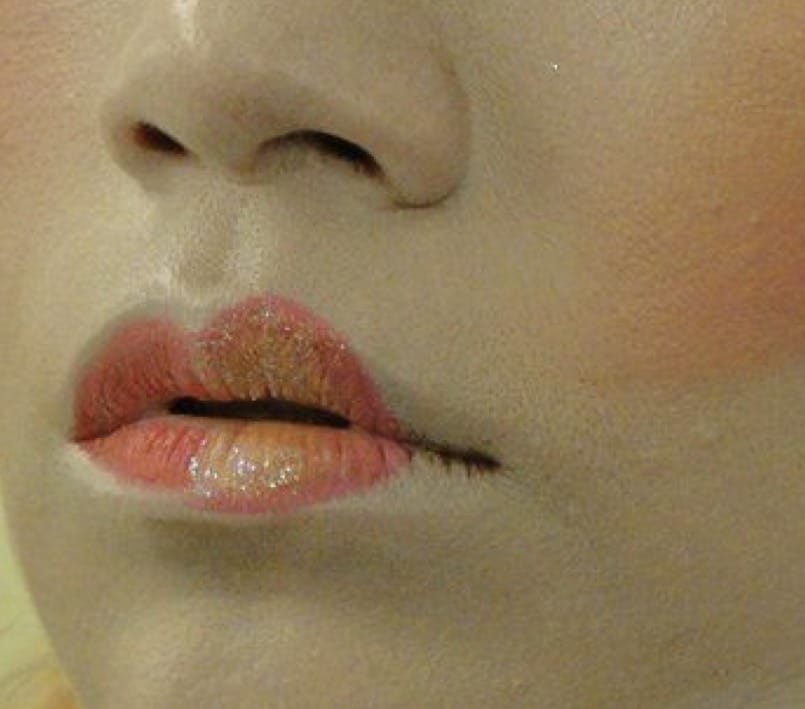Breast Implant Illness (BII): What We Know, What We Don’t—and Why That Distinction Matters

The Short Answer

Breast implant illness (BII) describes a constellation of systemic symptoms some women with breast implants report—fatigue, brain fog, joint and muscle pain, headaches, hair loss, and more. The FDA acknowledges these reports, but as of 2026 BII is not a formal medical diagnosis and there is no validated test that confirms it. Large studies after the 1990s silicone controversy did not establish that silicone implants cause classic connective-tissue disease; newer work may show associations between implants and systemic symptoms, but association is not causation. Silicone is also ubiquitous in personal-care products and the environment. Many patients report improvement after explant—that relief can be real—without proving why they improved. Wanting implants removed is reason enough for surgery; promising a cure for every attributed symptom is not honest consent.

Key Takeaways

  • BII names real, self-reported symptoms—not a formal diagnosis with a confirmatory biomarker.
  • 1990s-era large studies (including the Nurses’ Health Study and a NEJM meta-analysis) did not show a meaningful increase in major connective-tissue diseases from silicone implants.
  • If “silicone” is the proposed culprit, ask which silicone, from where, at what dose, by what route, and by what mechanism—not only the two implants in the room.
  • High rates of patient-reported improvement after explant deserve study; they do not, by themselves, prove biological causation.
  • Explant on request is legitimate care. Guaranteeing symptom resolution is not a promise medicine can currently make.
  • “We don’t know yet” must cut both ways—it cannot mean both ignorance and established guilt.

Few subjects in aesthetic plastic surgery generate as much emotion—or as much online certainty—as breast implant illness, commonly abbreviated BII.

Women who describe BII may be genuinely suffering. Some report dramatic improvement after their breast implants are removed. Others do not. Meanwhile, social media can transform a complicated scientific question into something deceptively simple: I had implants. I became sick. The implants made me sick.

Perhaps they did.

But medicine requires us to distinguish what is possible, what is associated, and what has actually been demonstrated.

That distinction is not medical gaslighting. It is the purpose of science.

My goal here is neither to defend breast implants nor to dismiss women who believe their implants have made them ill. I implant breast implants. I remove them. I revise them. I have no philosophical allegiance to a silicone bag.

Instead, I want to take some of the temperature out of an understandably emotional discussion and examine what we actually know—and, just as importantly, what we don’t.

What Is Breast Implant Illness?

Breast implant illness is a term used by patients and physicians to describe a broad constellation of systemic symptoms reported by some women with breast implants.

Commonly reported symptoms include:

  • Chronic fatigue
  • “Brain fog,” memory or concentration problems
  • Joint and muscle pain
  • Headaches
  • Hair loss
  • Weight changes
  • Anxiety and depression
  • Sleep disturbances
  • Various other nonspecific systemic complaints

The FDA acknowledges these reports in women with both silicone- and saline-filled implants. But as of 2026, the FDA also states something critically important: BII is not recognized as a formal medical diagnosis, and there are no specific tests or recognized diagnostic criteria that define it.

In other words, there is presently no blood test, imaging study, antibody, pathological finding or other validated biomarker that allows a physician to say:

“This patient has breast implant illness.”

That doesn’t mean the symptoms aren’t real.

It means we don’t yet know what those symptoms represent—or, in an individual patient, what caused them.

We’ve Been Down a Similar Road Before

I was practicing plastic surgery during the great silicone breast implant controversy of the 1990s.

At the time, silicone implants were accused of causing rheumatoid arthritis, lupus, scleroderma, Sjögren’s syndrome and other connective-tissue and autoimmune diseases. Media attention and litigation exploded, and silicone implants were restricted in the United States outside controlled circumstances.

The controversy also triggered an extraordinary amount of research.

In 1995, investigators analyzing 87,501 women in the Nurses’ Health Study found no association between breast implants and defined connective-tissue diseases. Importantly, their follow-up data largely preceded the widespread media attention surrounding the controversy.1

In 2000, a New England Journal of Medicine meta-analysis combined 20 epidemiologic studies and again found no evidence that breast implants produced a meaningful increase in the major connective-tissue diseases being investigated.2

The FDA today similarly states that it has not detected an association between silicone gel-filled breast implants and connective-tissue disease.7

That does not prove that implants cannot cause systemic symptoms through some mechanism that we have yet to understand.

It does demonstrate why anecdote and biological causation cannot be treated as synonyms.

The 1990s Implant Litigation Is Worth Remembering

The history is particularly interesting because the scientific debate did not occur in a vacuum.

A 2010 article in the AMA Journal of Ethics reviewed the extraordinary breast-implant litigation of the 1990s and described the collision among public fear, litigation, physicians, manufacturers and emerging scientific evidence. It noted that early jury verdicts occurred before the epidemiological evidence matured and that later independent scientific reviews increasingly failed to support the sweeping autoimmune claims being made at the time.8

Some historical implant research did have industry involvement, and potential conflicts of interest deserve scrutiny. But the evidence cannot accurately be dismissed as simply “research paid for by breast implant companies.” Major work was also supported by government and independent sources.

So yes: follow the money. But follow it in both directions.

Industry conflicts matter. So do litigation conflicts, advocacy bias and professional incentives.

Science ultimately has to stand on whether findings can be reproduced by different investigators, in different populations, using different methods.

The Pesky Little Problem: Silicone Is Everywhere

Here is another part of the discussion that rarely receives enough attention.

Silicone is ubiquitous.

Silicone isn’t one chemical. It is a family of silicon-oxygen-containing compounds with dramatically different molecular sizes and properties.

Small cyclic volatile methylsiloxanes such as D4, D5 and D6 have been demonstrated in tissues surrounding silicone breast implants. Gel bleed and migration of certain low-molecular-weight siloxanes through an intact implant shell are real phenomena.5

But those same families of siloxanes aren’t unique to breast implants.

They are widely encountered in our everyday environment and are used in personal-care products, including cosmetics, antiperspirants and particularly hair-care products. Studies of indoor environments identify personal-care products as an important source of human exposure to volatile methylsiloxanes.

Bottle and label: silicones in everyday hairspray and foundation.

Pantene Texture Building Hairspray bottle beside an ingredient callout highlighting PEG-12 dimethicone and related silicones
Hairspray — bottle and silicones. Pantene Texture Building Hairspray (product shot) paired with published INCI highlights: PEG-12 dimethicone and related -cone/-oxane silicones commonly listed on hairsprays in this category. Formulas vary by SKU—check your can.
Lancôme Teint Idole Ultra Wear foundation bottle beside an ingredient callout highlighting dimethicone, PEG-10 dimethicone, and trimethylsiloxysilicate
Foundation — bottle and silicones. Lancôme Teint Idole Ultra Wear (Sephora product shot) with silicones from the published DailyMed/Ulta ingredient list: dimethicone, PEG-10 dimethicone, trimethylsiloxysilicate, hydrogen dimethicone, and related film-formers.

A particularly fascinating 2023 study actually measured emissions during ordinary hair-care routines. D5 was the predominant cyclic siloxane emitted. Under one modeled poorly ventilated bathroom scenario, the estimated cumulative D5 inhalation during a 20-minute hair-care routine reached approximately 17 milligrams. Turning on the exhaust fan substantially reduced that exposure.6

That certainly does not prove that hairspray is safer or more dangerous than a breast implant. These are completely different exposure circumstances and should not be treated as a head-to-head toxicological comparison.

But it raises an important scientific question.

If the proposed culprit is simply “silicone,” then we have to ask:

Which silicone? From where? At what dose? By what route? Over what period of time? And through what biological mechanism?

Simply pointing at the two most obvious pieces of silicone in the room and declaring those twins guilty doesn’t answer those questions.

Woman holding two silicone breast implants in front of her chest
Though a photograph is able to capture an association by proximity, it is unable to expose causality which only hard-and-fast data can.

Association is not causation.

“But I Felt Better After My Implants Were Removed”

This is perhaps the most compelling argument made by women who believe they have experienced BII.

And it deserves to be taken seriously.

A 2025 systematic review and meta-analysis involving 33 studies and more than 6,000 women reported that approximately 82% of patients reported some symptom improvement following explantation. Another systematic review found similarly high rates of patient-reported improvement.3

That is interesting.

It deserves further study.

But it still does not, by itself, establish causation.

A 2026 systematic review and meta-analysis reached a more cautious conclusion: among patients categorized as having BII/systemic symptoms, most did not achieve complete resolution, average improvement was more moderate, and the authors emphasized considerable heterogeneity among the underlying studies.4

This is precisely why study design matters.

Imagine spending months or years convinced that a foreign object inside your body is poisoning you. You research it extensively. Perhaps you join online communities populated by people experiencing similar symptoms. Eventually, you undergo surgery and the object you have come to fear is finally removed.

The surgery goes well.

Someone then asks:

“Do you feel better?”

That is hardly a double-blinded experiment.

Expectancy effects, placebo effects, reversal of a nocebo effect and confirmation bias are legitimate potential confounders. That doesn’t mean the patient’s improvement isn’t genuine. It means improvement alone cannot tell us why she improved.

I sometimes describe this as the surgical equivalent of confirmation bias.

The FDA takes an appropriately cautious position: some women report improvement or resolution following explantation, but the cause of these systemic symptoms and the degree to which they are related to the implants remain unclear.7

There is an important lesson here:

“We don’t know yet” has to cut both ways.

It cannot be used simultaneously to argue that science doesn’t understand BII and that science has therefore established that implants caused it.

What I Tell My Patients Who Want Their Implants Removed

When a woman comes to me and says:

“Doctor, I believe I have breast implant illness and I want my implants removed.”

My answer is quite straightforward.

You’ve come to the right place. I’m a plastic surgeon. Removing breast implants is part of what I do.

If a woman no longer wants implants in her body, that alone is a legitimate reason to remove them. She doesn’t need to convince me that she has BII.

But before surgery, I owe her something considerably more valuable than agreement:

informed consent.

I can promise to remove her implants.

I cannot honestly promise that removing them will cure her fatigue, brain fog, joint pain, headaches, anxiety or whatever systemic symptoms she has attributed to them.

If she understands that uncertainty and still wants her implants removed?

Absolutely. Off we go.

Because my responsibility as a surgeon isn’t to tell a patient what she wants to hear—or what the implant industry, plaintiffs’ attorneys, Facebook groups or anyone else wants her to hear.

It is to tell her what we know, what the evidence suggests, and what we still don’t know.

That isn’t dismissing women’s symptoms.

It is taking them seriously enough not to pretend that medicine has answers it does not yet possess.

The Bottom Line on Breast Implant Illness

Breast implant illness remains an evolving and controversial area of medicine.

Women reporting these symptoms deserve to be heard. Their symptoms should be investigated rather than automatically attributed to implants—or automatically dismissed. And women who decide they no longer want breast implants should have access to thoughtful explantation counseling.

At the same time, medicine should resist replacing one form of dogma with another.

The emerging literature suggesting an association between implants, systemic symptoms and improvement after explantation deserves serious investigation. In fact, a 2025 meta-analysis found BII-type symptoms were reported more frequently among women with implants for several symptom categories. That is a signal worth studying, not ignoring.3

But a signal is the beginning of a scientific investigation, not the end of one.

Perhaps we will ultimately identify an inflammatory, immunological, microbial, genetic or other mechanism that explains systemic symptoms in a susceptible subset of women. Perhaps what we currently call BII will ultimately prove to encompass several different conditions.

I don’t know. Neither does anyone else yet.

And for the moment, that may be the most scientifically honest answer of all.

Frequently Asked Questions

Is breast implant illness a recognized medical diagnosis?

Currently, the FDA states that BII is not recognized as a formal medical diagnosis and that there are no specific diagnostic tests or recognized criteria defining it.7

What are the most common BII symptoms?

Reported symptoms include fatigue, brain fog, joint and muscle pain, hair loss, weight changes, anxiety and depression.

Do symptoms improve after breast implant removal?

Many patients report improvement following explantation, and systematic reviews have documented substantial patient-reported improvement. However, studies are heterogeneous, and improvement following removal does not by itself establish the biological mechanism responsible.3,4

Is there proof that breast implants cause autoimmune disease?

The FDA currently states that it has not detected an association between silicone gel-filled breast implants and connective-tissue disease, although research into systemic symptoms associated with implants continues.7

Does breast implant removal require a total capsulectomy for BII?

The evidence does not currently establish that every patient seeking explantation for systemic symptoms requires total capsulectomy. The appropriate surgical approach should be individualized according to implant and capsule findings, medical indications and patient circumstances.

Selected Scientific References

  1. Sánchez-Guerrero J, et al. Silicone Breast Implants and the Risk of Connective-Tissue Diseases and Symptoms. New England Journal of Medicine. 1995;332:1666–1670.
  2. Janowsky EC, Kupper LL, Hulka BS. Meta-analyses of the Relation Between Silicone Breast Implants and the Risk of Connective-Tissue Diseases. New England Journal of Medicine. 2000;342:781–790.
  3. Ferreira S, Barros AS, Marques M. Breast Implant Illness: Symptoms, Outcomes with Explantation and Potential Etiologies—A Systematic Review and Meta-analysis. Aesthetic Plastic Surgery. 2025.
  4. Cuenca-Pardo J, et al. Breast Implant Explantation and Capsulectomy in Symptomatic Patients. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2026.
  5. Flassbeck D, et al. Determination of Siloxanes, Silicon, and Platinum in Tissues of Women With Silicone Gel-Filled Implants. Analytical and Bioanalytical Chemistry. 2003.
  6. Jung N, et al. Siloxane Emissions and Exposures During the Use of Hair Care Products in Buildings. Environmental Science & Technology. 2023.
  7. FDA. Medical Device Reports for Systemic Symptoms in Women with Breast Implants.
  8. Schleiter KE. Silicone Breast Implant Litigation. AMA Journal of Ethics. 2010.

Randal D. Haworth, MD, FACS
Board-Certified Plastic Surgeon | Beverly Hills


The Great Filler Dissolving Obsession

The Short Answer

Hyaluronidase is an enzyme used to dissolve hyaluronic acid (HA) fillers such as Juvéderm and Restylane. It can be extremely useful for treating misplaced or excessive filler, persistent swelling and the blue-gray discoloration known as the Tyndall effect. But the presence of residual filler on ultrasound or MRI does not necessarily mean that every trace of it needs to be removed. The goal should be correction of the clinical problem—not simply elimination of an imaging finding. In many cases, selective hyaluronidase treatment followed by careful massage and reassessment can produce a better aesthetic result than repeatedly attempting to dissolve every detectable molecule of filler.

Hyaluronidase dissolves hyaluronic acid–based fillers by hydrolyzing the HA polymer — breaking it down so the body can clear it. Recent literature has challenged even the terminology of “dissolving” filler. Harris and Weiner argue that hyaluronidase may be better understood as modifying a complex filler-tissue system rather than predictably eradicating every molecule of HA. Importantly, clinical improvement may occur even when ultrasound or MRI continues to demonstrate residual filler.1

Key Takeaways

  • Hyaluronidase can selectively dissolve unwanted hyaluronic-acid filler.
  • Tyndall effect is a blue-gray discoloration that can occur when HA filler is placed too superficially.
  • Not every residual pocket of filler visible on ultrasound or MRI requires treatment.
  • Repeated attempts to eliminate every trace of filler may create additional swelling, tissue changes and dissatisfaction.
  • Clinical examination should determine whether detected filler is actually causing an aesthetic problem.
  • In selected cases, careful massage and molding after hyaluronidase can be an important part of correction.

Hyaluronic acid fillers such as Juvéderm and Restylane can produce beautiful results—and when they don’t, hyaluronidase can often correct the problem remarkably well.

But somewhere along the way, “dissolving unwanted filler” has evolved into something quite different: a quest to hunt down and eradicate every detectable trace of filler from the face.

And I think we need to talk about it.

Unless you have been living in a hermetically sealed cave for the past 20 years, you have probably heard of hyaluronic acid (HA) fillers such as Juvéderm and Restylane.

Hyaluronic acid itself is hardly an exotic substance. It is a naturally occurring sugar found throughout the human body—in our skin, connective tissues, joints and even our eyes. Its ability to attract and retain water is one reason HA fillers are so useful for restoring volume, softening contours and reshaping certain areas of the face.

Most of the time, when properly selected and properly injected, they work very well.

But not always.

When Good Filler Goes Bad

Hyaluronic acid is hydrophilic—it attracts water. That is generally useful, but in certain areas, particularly around the eyes, too much filler or filler placed at the wrong depth can create persistent puffiness or edema.

HA filler can also sometimes produce a characteristic bluish-gray discoloration, particularly when placed too superficially. This is commonly referred to as the Tyndall effect.

And frustratingly, these problems don’t necessarily announce themselves while you’re still sitting in the injector’s chair. Swelling, contour irregularities and unwanted fullness can become apparent days or even a week or two later.

Fortunately, HA fillers have one enormous advantage over many other injectable materials:

We have an eraser.

Tyndall effect before hyaluronidase
Before
Under-eye Tyndall effect / bag from hyaluronic acid filler (before hyaluronidase).
Improvement after hyaluronidase
After
After hyaluronidase with careful massage and molding.

Before and after treatment of the Tyndall effect. Improvement followed targeted hyaluronidase with careful massage and molding.

Hyaluronidase: The Filler Eraser

Hyaluronidase is an enzyme that breaks down hyaluronic acid. Commercial preparations include products such as Hylenex and Vitrase, among others.

I often describe hyaluronidase to my patients as a pencil eraser.

If I’ve performed a filler treatment and several days later notice a little excess fullness or an area that needs refinement, a carefully placed amount of hyaluronidase can often correct it quickly and effectively.

I also use hyaluronidase before certain facial surgical procedures when previously placed filler is obscuring the anatomy I actually need to evaluate or treat.

Used thoughtfully, it is an extraordinarily useful tool.

The trouble starts when the pencil eraser becomes a belt sander.

The New Obsession With Dissolving Everything

Increasingly, I see patients who don’t simply want an unattractive area of filler corrected.

They want every molecule of filler removed from their face.

Some arrive after months of repeated dissolving sessions. They have undergone ultrasounds, MRIs or other imaging studies searching for residual pockets of filler.

A scan identifies another tiny area.

That area gets injected with more hyaluronidase.

Another scan is obtained.

Something else is found.

And down the rabbit hole we go.

More appointments. More scans. More dissolving. More swelling. More anxiety. More money.

Yet when I actually look at the patient, there may be very little—or sometimes nothing—visibly wrong.

At some point, the pursuit itself becomes the problem.

Interestingly, this isn’t merely theoretical. A retrospective study of 157 treated orbits found that while 59% achieved a satisfactory result after hyaluronidase, 24% required additional treatment and 18% reported post-treatment facial changes such as hollowing—a phenomenon the authors termed “posthyaluronidase syndrome.” This does not prove that hyaluronidase permanently damages one’s native tissues, as some corners of social media would have you believe. But it does reinforce a rather basic aesthetic principle: more treatment is not necessarily better treatment.3

Hyaluronic Acid Is Not a Metastatic Disease

This is where some perspective is desperately needed.

Residual hyaluronic acid filler is not cancer. It is not a metastatic disease that must be hunted down and banished from every corner of the face.

The objective of aesthetic medicine is not to produce an MRI demonstrating absolute molecular purity.

The objective is to make the patient look better.

That distinction sounds ridiculously obvious.

Apparently, it isn’t.

Imaging can unquestionably be useful. Ultrasound, for example, can help identify the location and depth of previously injected material in selected situations. MRI may reveal material or tissue changes that aren’t obvious on examination.

But the existence of something on an image does not automatically mean that it is producing an aesthetic problem—or that treating it will improve the patient’s appearance.

Which brings me to the sophisticated diagnostic technology I use most frequently.

My Favorite Imaging Device: My Eyes

Patients sometimes ask:

“What makes you successful at dissolving difficult filler? Are you using MRI? Ultrasound? Some special imaging technology?”

Those technologies certainly have their place.

But my primary diagnostic instrument remains decidedly low-tech:

My eyes.

If I see abnormal puffiness, a blue-gray Tyndall effect, contour distortion or meaningful asymmetry that appears related to filler, I treat it.

If I don’t see a problem, I generally leave it alone.

And, perhaps more importantly, I encourage the patient to leave it alone too.

Because I’m treating a face, not an MRI.

An imaging study should help answer a clinical question. It should not automatically create a new clinical problem simply because it detected something.

Hyaluronidase Dissolves. Massage Sculpts.

This isn’t merely philosophical restraint. Published guidance on Tyndall effect specifically describes selective dissolution of the superficial offending HA layer without removing the entire filler deposit. The literature also recognizes massage following hyaluronidase as part of managing certain HA gels. In other words, the objective is correction—not molecular extermination.2

There is another element of successful filler correction that receives surprisingly little attention: massage and molding.

Hyaluronidase is not magic water.

You don’t simply inject a few drops, walk away and wait for perfection to occur.

When appropriate, careful manipulation of the treated area—from deeper tissues toward the surface—can be an important part of achieving a smooth, controlled correction.

In my experience, thoughtful massage and molding can sometimes be every bit as important as where the enzyme itself is placed.

The goal isn’t indiscriminate destruction of filler.

It is controlled correction.

That requires anatomy, judgment, examination and, yes, occasionally knowing when to stop.

Dissolve the Problem—Not the Patient’s Peace of Mind

There is nothing wrong with wanting poorly placed filler corrected. I do it regularly.

There is nothing wrong with using imaging when the clinical situation genuinely warrants it.

And there is certainly nothing wrong with hyaluronidase. It remains one of the great advantages of HA fillers precisely because it gives us a degree of reversibility that many aesthetic treatments simply don’t have.

But there is an enormous difference between correcting a visible problem and embarking upon an endless search for microscopic remnants of something simply because modern imaging technology is capable of finding them.

More information does not always mean more treatment.

Sometimes the most sophisticated decision a physician can make is to look at the patient and say:

“That looks good. Leave it alone.”

In aesthetic medicine, as in much of medicine, the simplest solution is often the best one.

And occasionally, the hardest procedure to perform is no procedure at all.

Selected Medical References

  1. Harris S, Weiner S. Reframing Hyaluronidase in Aesthetic Medicine: From “Dissolving Filler” to “Modifying Filler.” Aesthetic Surgery Journal. 2026;46(6):NP51–NP54. DOI: 10.1093/asj/sjag022
  2. Nonvascular Complications of Injectable Fillers—Prevention and Management. https://pmc.ncbi.nlm.nih.gov/articles/PMC7822713/
  3. The Posthyaluronidase Syndrome: Dosing Strategies for Hyaluronidase in the Dissolving of Facial Filler and Independent Predictors of Poor Outcomes. https://pubmed.ncbi.nlm.nih.gov/38655103/

Randal D. Haworth, MD, FACS
Board-Certified Plastic Surgeon | Beverly Hills

How Custom Chin Implants Are Transforming Facial Harmony — Here’s What Top Surgeons Won’t Tell You


The Art and Science of Chin Enhancement: Balancing Beauty, Restoring Proportion

As a plastic surgeon with a global clientele, I often say: chin enhancement may not be necessary—but in facial aesthetics, necessity and desire can merge beautifully. Let’s explore why.

Why the Chin Matters

From the front, the chin defines the proportions of the upper, middle, and lower facial thirds. A recessed chin can make the face appear wider, disrupt harmony, and cast vertical shadows from the mouth corners toward the jawline—subtle signs of “pseudo‑jowls” long before they appear.

Before-and-after comparison of an anatomic extended chin implant showing reduced vertical shadow wings between the lower lip and chin, improving lower face harmony.

Anatomic Extended Chin Implant — Before & After:
The “shadow wings” that extended from the corners of the lower lip toward the chin have been significantly reduced, restoring smoother, more harmonious lower facial contours.The patient also underwent an upper lip lift
.

From the profile, a properly aligned chin should fall along a vertical plumb line with the nose. A weak chin can contribute to submental skin laxity and even a flaccid lower lip that exposes the lower teeth.

Before-and-after images of chin implant surgery correcting a recessed chin, lifting a forward-hanging lower lip, and tightening loose submental skin.

Recessed Chin Correction with Chin Implant — Before & After:
Marked improvement in chin projection, resolution of flaccid forward-hanging lower lip, and tightening of loose submental skin after chin augmentation.
 

Enhanced Insights from Recent Trends

  • Rising demand for chin implants in 2025: Surgeons are seeing increasing popularity for chin implants due to their ability to refine face shape and define the jawline with minimal downtime .
  • Custom implants using CAD/3D‑printing: Personalized implants designed via CAD and 3D modeling offer unmatched precision and harmonious results  .
  • Preference for natural aesthetics: Patients increasingly favor subtle, authentic enhancements over overly dramatic looks—often referred to as the shift from Kardashian‑style to more natural facial harmony  .
  • Advantages of implants vs. fillers: Implants offer more dramatic and permanent results, especially for those ready for lasting change. Fillers remain a great trial option or for those seeking modest, temporary enhancement .

Refined Surgical Options

  1. Dermal and Fat Fillers

    • Temporary fillers (like hyaluronic acid or calcium hydroxyapatite) or permanent options (such as Bellafill or autologous fat) offer non‑surgical chin enhancement, ideal for previewing outcomes  or as a relatively simple, non-invasive methods for mild to moderate issues Jaw fillers .

  2. Sliding Genioplasty (Advancement Osteotomy)

    A versatile technique moving the chin bone itself for structural change. Though powerful, it carries risks like step‑offs, lower lip laxity, and disruption of the mentalis muscle—hence my caution toward this approach. Sliding genioplasty

  3. Chin Implants (My Preferred Method)

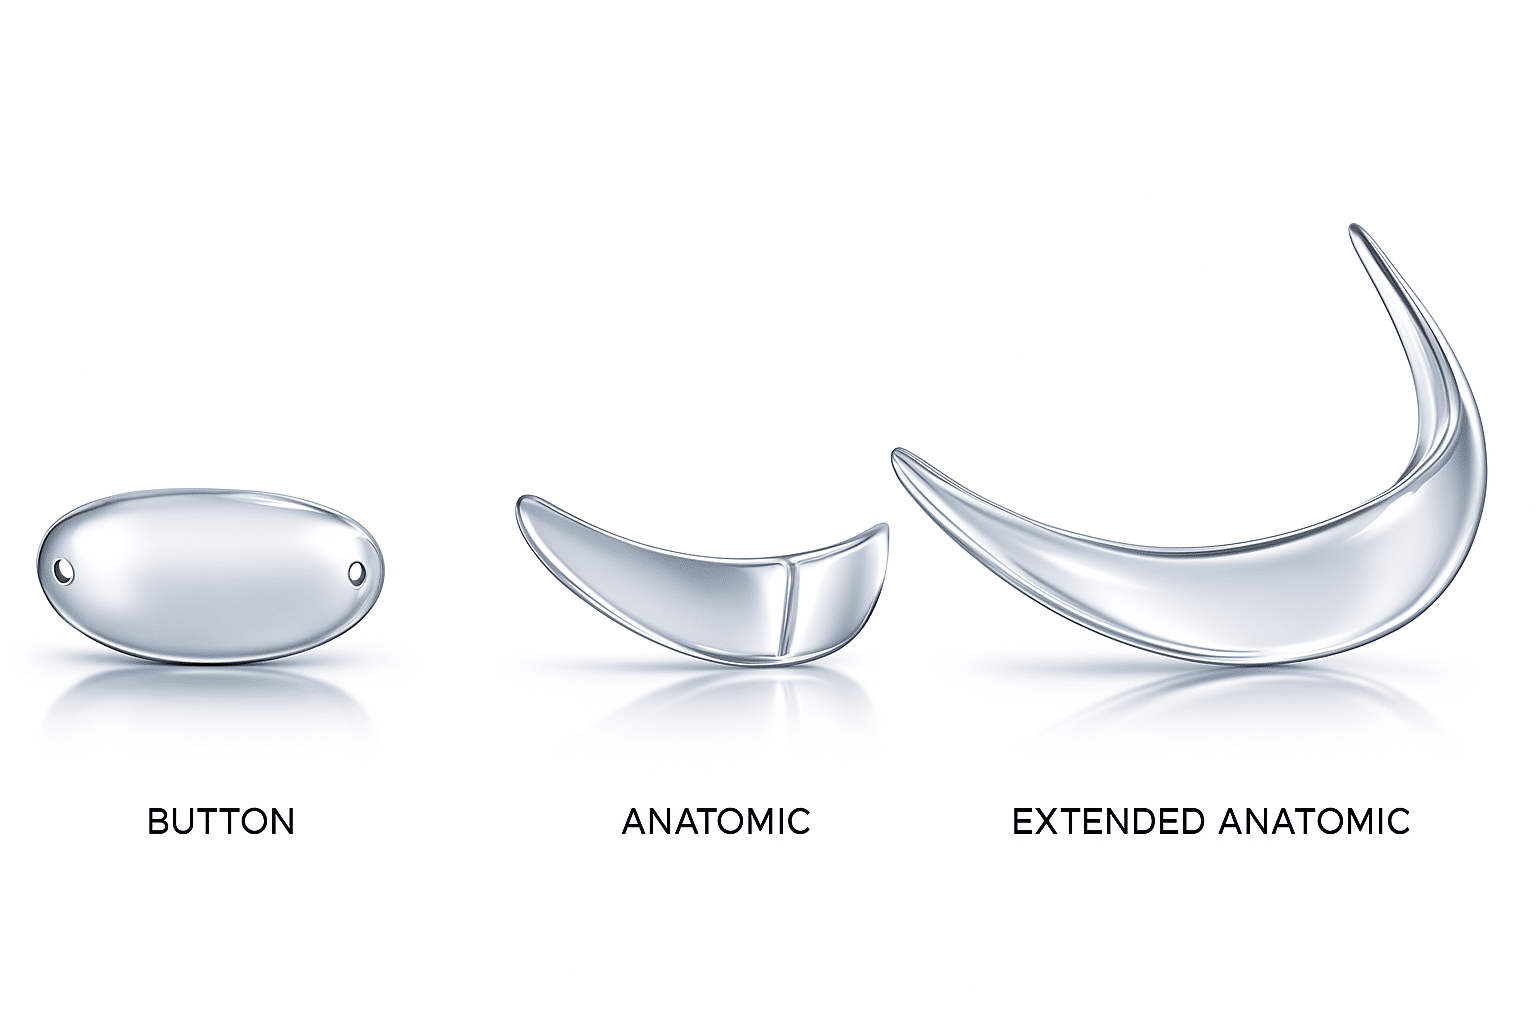
    • I favor solid silicone implants that I sculpt for personalized fit—whether a button style or an extended “boomerang” design to restore jawline flow. Their placement can even lengthen the lower face and improve posture of submental tissue. I personally customize the implant to both size and shape to not only account for underlying asymmetry of the bony mandible (on which it will sit) but also the asymmetrical overlying soft tissue (which will form the roof of the pocket). Pre-fabricated Chin implants only taken into account asymmetry of the bone and not of the soft tissue. Chin augmentation
    • Modern implants offer long-lasting, customizable results, minimal visible scarring, and enhanced facial proportions  
    • With proper case selection and surgical technique, complications are rare, and implants remain a go-to for enduring aesthetic refinement.

Custom chin implants in three styles—Button, Anatomic, and Extended Anatomic (Boomerang)—displayed side by side on a white background, used for tailored jawline contouring and improved facial proportions.

Comparison of three custom chin implant designs—Button, Anatomic, and Extended Anatomic (Boomerang)—crafted for personalized jawline contouring and enhanced facial harmony.

Beyond Aesthetics: Function and Form

A well-executed chin augmentation doesn’t just create a stronger jawline—it can smooth shadowing, lift a flaccid lower lip, and tighten loose submental skin. Done thoughtfully, it transforms the lower face into a more confident, balanced, and aesthetically cohesive whole. In the end, a well-proportioned chin plays an integral role geometry, balance, and how you carry yourself in the world. Whether you’re chasing a sharper jawline, banishing those telltale shadows, or simply giving your lower lip the nudge it’s been begging for, chin enhancement can be the quiet hero of facial aesthetics. 

Randal D. Haworth, MD, FACS / Board-Certified Plastic Surgeon | Beverly Hills
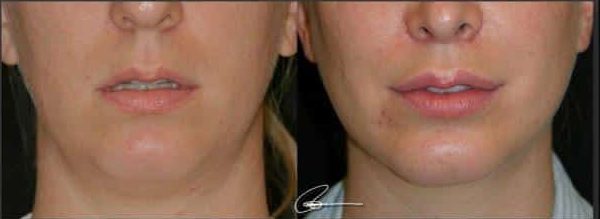
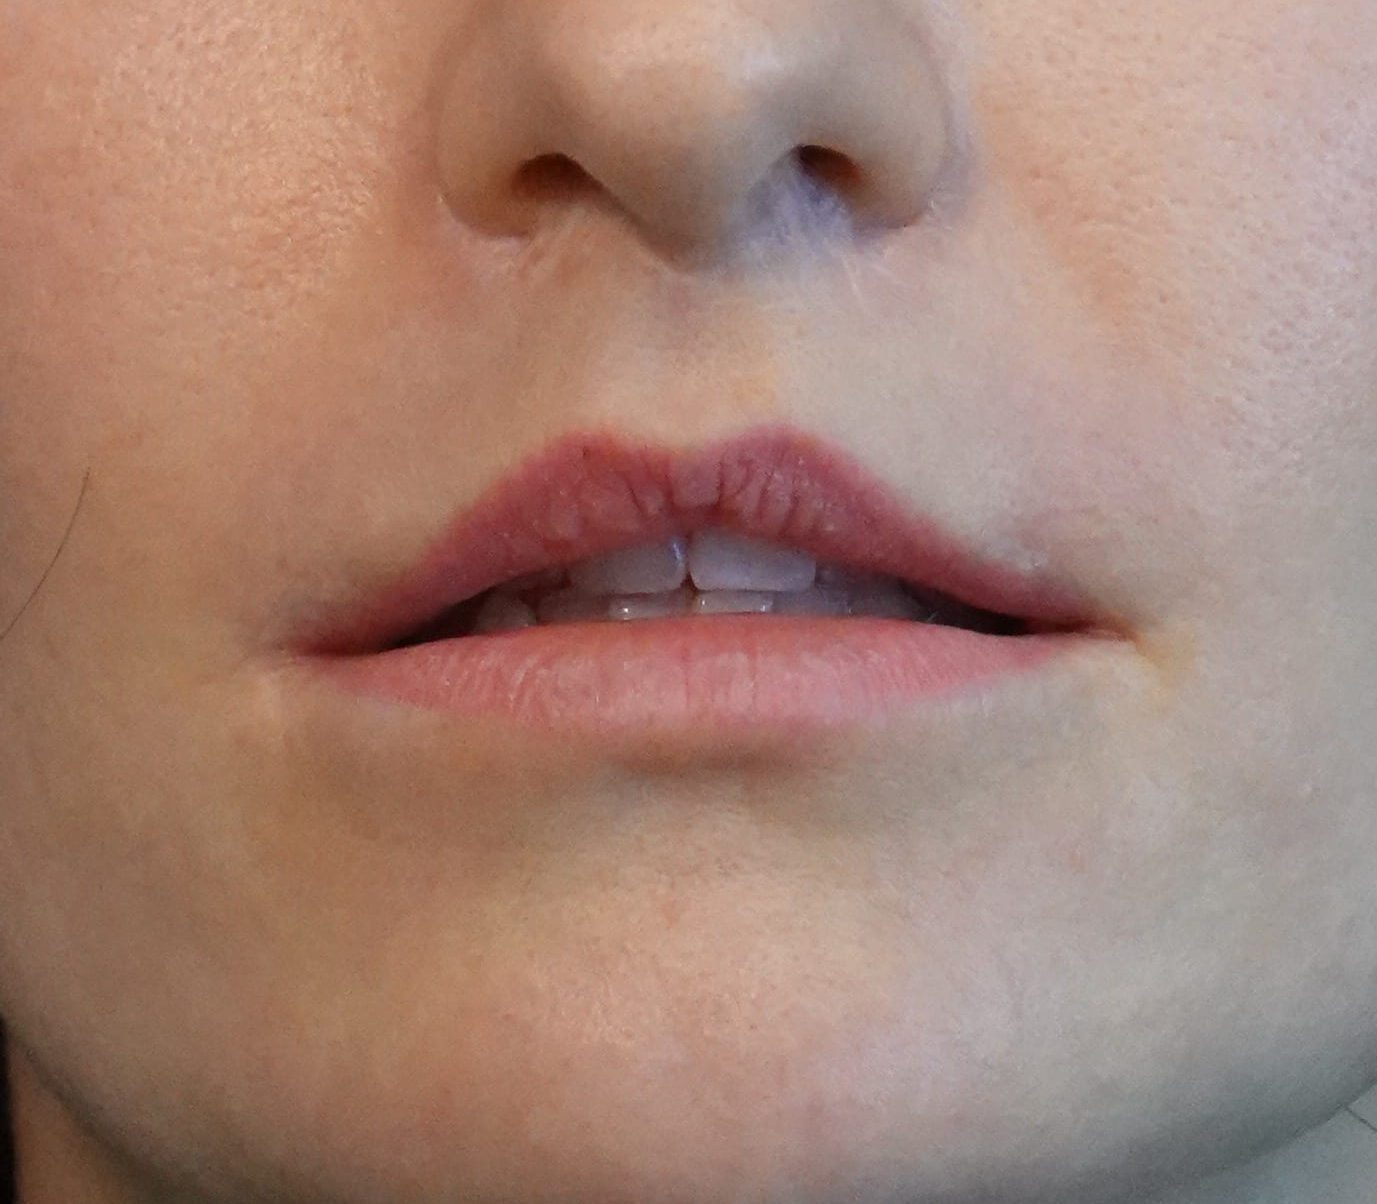
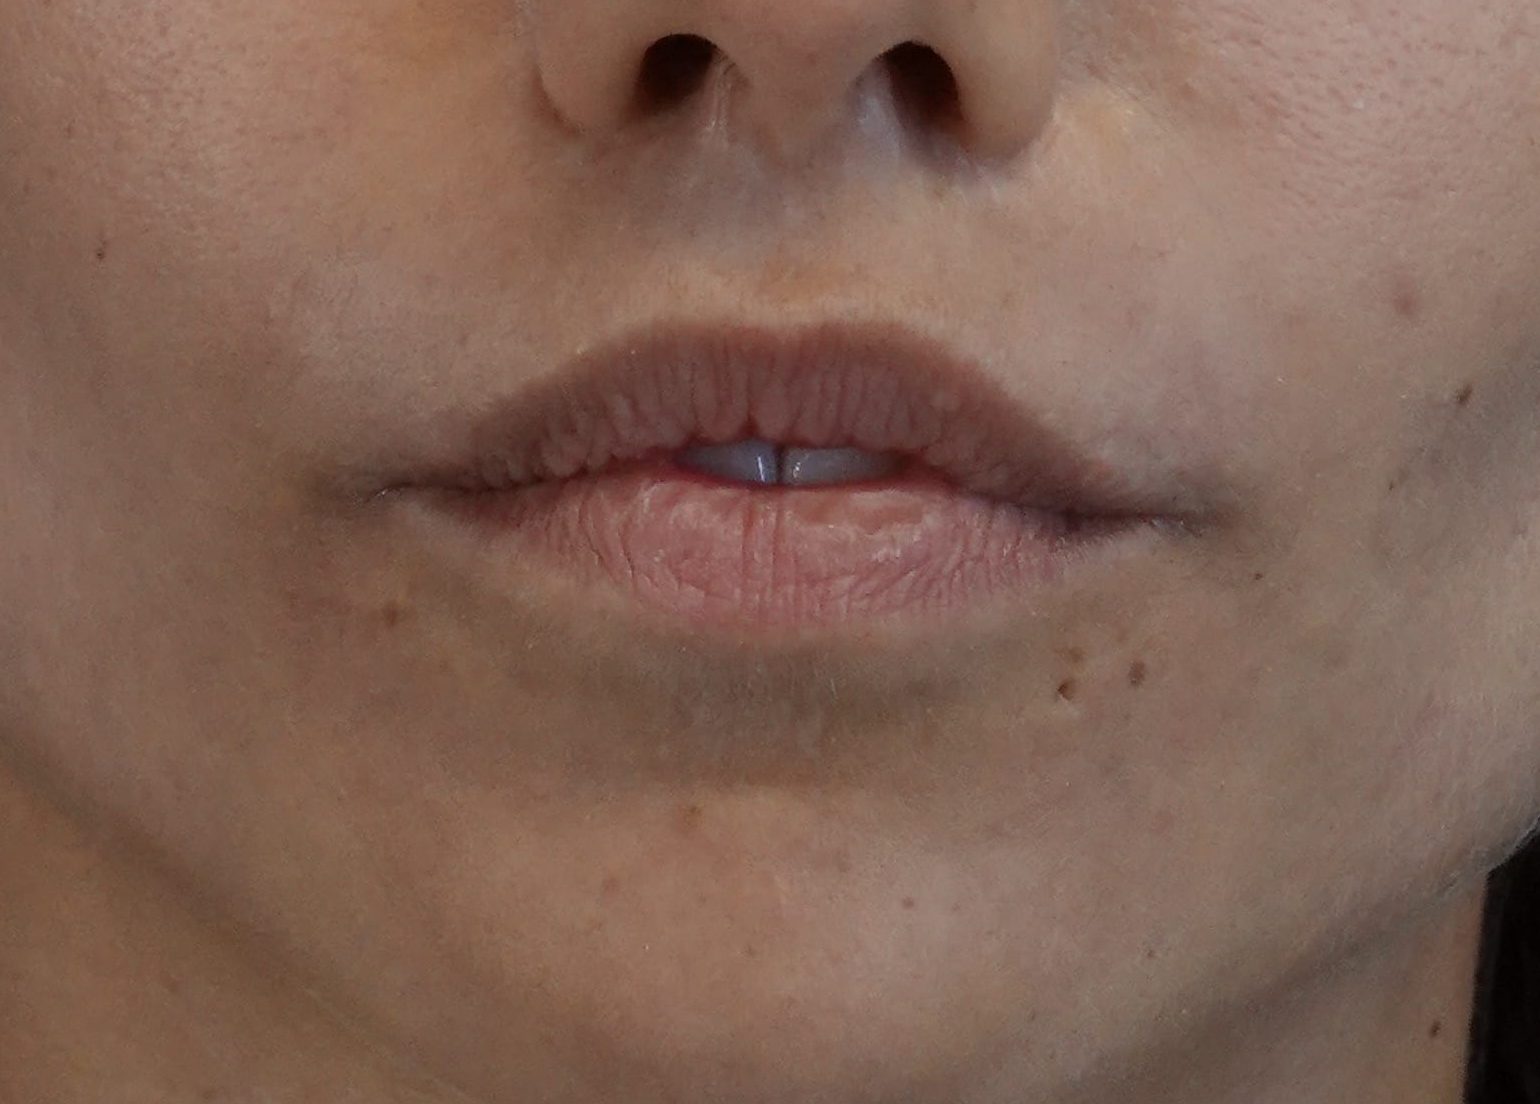
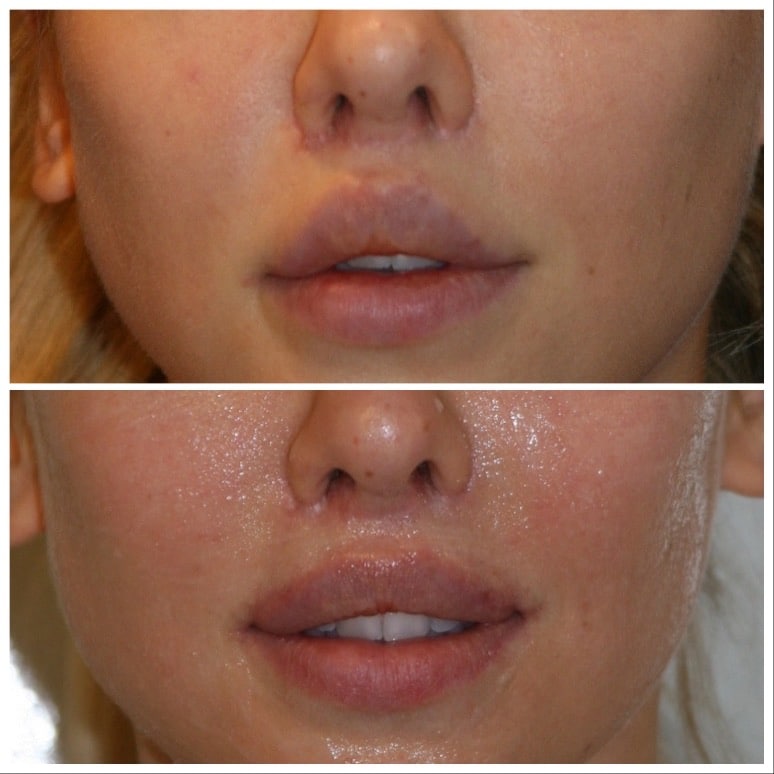
The “Neonatal Deformity” is the Upper Lip Lift’s Unwanted Offspring

To think that when Dr. Randal Haworth started his practice over 30 years ago, he was one of only a handful of leading plastic surgeons who specialized in lip reshaping surgery. Now, as one of the world’s most renowned lip lift experts, he has witnessed how upper lip lifts have exploded in popularity thanks to the influence of social media on the young and old alike. However, as with any trend, unintended consequences may arise such as the “neonatal deformity,” which originates from the congenital Apostrophe Lip. I first described this latter labial morphology in a chapter I authored for “Aesthetic Surgery of the Facial Skeleton”, a textbook edited by Dr. Steven Baker in 2019.

What Is an Apostrophe Lip?

You might not recognize the name, but you’ve likely seen the effect: the pink vermilion (the visible part of the lip) is full and prominent only in the center, while the outer thirds taper off or even disappear. This narrowing gives the mouth a stylized, doll-like appearance reminiscent of Kabuki makeup, where the lips are intentionally painted small and central.

While deliberate in performance art, this effect is aesthetically unflattering when unintentional—and unfortunately, upper lip lifts performed without addressing corner anatomy often exaggerate this deformity.

Kabuki performance artist's lips
Kabuki-style makeup mimicking an Apostrophe lip — note the abrupt loss of vermilion toward the corners, creating a slit-like mouth.

Kabuki lips
Another example of a stylized Kabuki “rosebud” mouth, often unintentionally replicated by improper upper lip lifts.

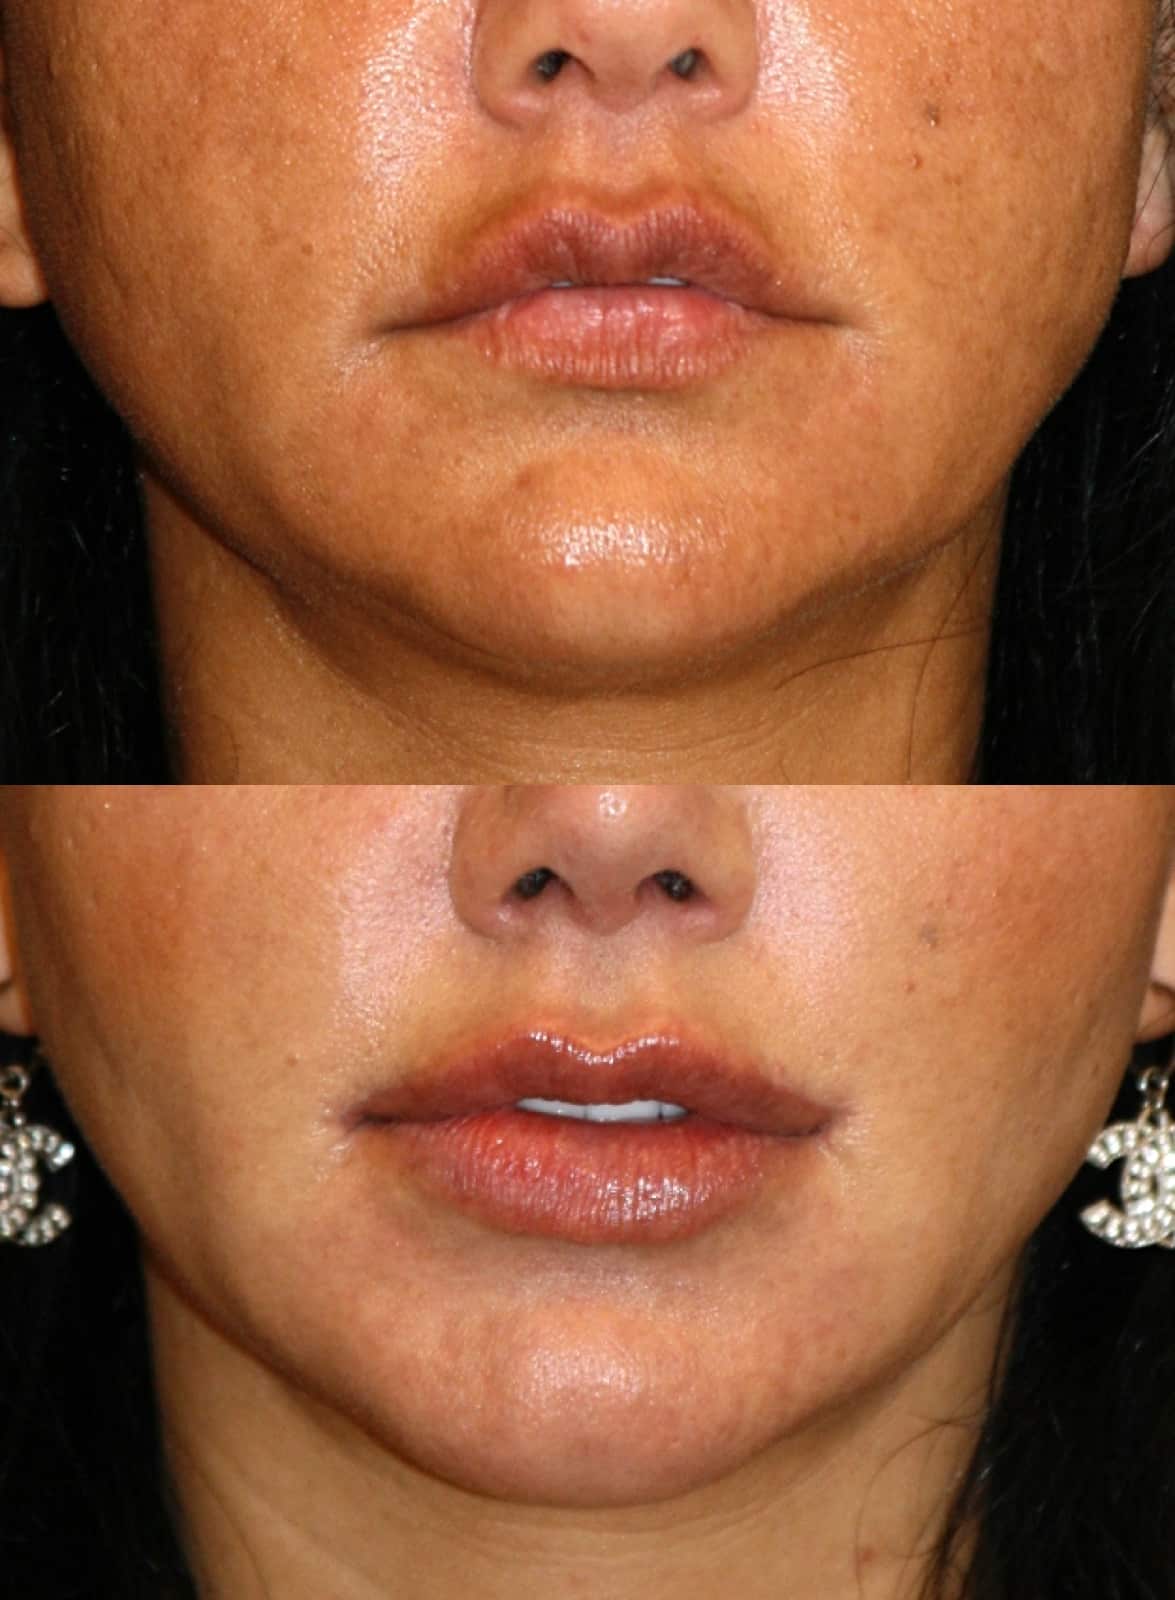
Overfilled lips due to both patient and practitioner perception drift
Before and after correction of an apostrophe lip using a medialized corner lip lift. This patient had chronic filler injections that exacerbated the deformity, narrowing the vermilion into a slit-like central zone.

How an Upper Lip Lift Can Create A Neonatal Lip

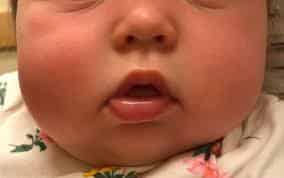
Lips of a Neonate
The neonatal deformity gets its name from the naturally recessed corners and centralized vermilion seen in newborns—charming in infants, but unflattering in adults.

Regardless of type, if an upper lip lift is performed without taking into account the oral commissures and lateral upper vermilion, a preexisting apostrophe lip can be exacerbated. The slope from the Cupid’s bow to the oral commissure (mouth corners) becomes unnaturally steep. The outer pink vermilion rolls inward or disappears entirely, leading to a pinched, slit-like appearance akin to that of a newborn. In essence, a neonatal deformity. Patients from around the world have come to me distressed by this outcome, often feeling disfigured and despondent.

Classic Neonatal deformity
Classic Neonatal lip deformity after an upper lip lift without regards to the oral commissures
A moderate neonatal lip deformity
A moderate neonatal lip deformity after an upper lip lift and an inadequate traditional corner lip lift

The Medialized Corner Lip Lift: A Powerful Solution

Enter the medialized corner lip lift—a precise, elegant surgical solution I’ve refined over the years to correct these issues. It not only repositions the corners of the mouth upward but also:

  • Restores lost vermilion by rolling it outward, eliminating that paradoxically tightlipped “rosebud” look.
  • Corrects asymmetry, which is present in the majority of mouths.
  • Improves the marionette folds (those stubborn lines running from the corners of the mouth downward) that facelifts often miss.
  • Softens the harsh slope from Cupid’s bow to oral commissure, restoring a balanced, natural curvature.

This is a high-precision procedure involving design and execution tolerances as fine as a quarter millimeter. But when done correctly, the results are not only restorative—they are transformative.

Neonatal lip deformity stemming from past upper lip lift.
This patient required a direct revision of her previous upper lip lift to correct pleating at the nasal base and a medialized corner lip lift to correct the neonatal deformity. A lower V–Y plasty was also performed.
Asymmetrical, neonatal, deformity after upper lip lift and simultaneous rhinoplasty
Another case of asymmetrical neonatal lip deformity after having undergone a previous upper lip lift simultaneous with a rhinoplasty. Dr. Randal Haworth corrected this with a medialized corner lip lift along with medical dermabrasion of her upper lip lift and nasal base/past rhinoplasty scars.. The vermilion was central and collapsed at the corners.

Final Thoughts

If you’ve undergone an upper lip lift and are unhappy with the corner distortion or feel like your lip looks smaller or more “pursed” than before—know that you’re not alone. These issues are more common than many realize, but they are entirely correctable.

Performed under local anesthesia, the medialized corner lip lift offers a sophisticated solution to restore harmony and confidence to your face.

Randal D. Haworth, MD, FACS / Board-Certified Plastic Surgeon | Beverly Hills
 

Reflecting on Iggy Azalea’s transformation

Iggy Azalea's

Iggy Azalea, the Australian rapper who has been a prominent figure in the music industry for over a decade, has undergone significant changes in her appearance over the course of her career. She burst onto the music scene with her iconic ice-blonde hair and fair skin, quickly earning her a fan base. However, her facial features and physique have transformed over the years.

According to Beverly Hills plastic surgeon Dr Randal Haworth, Azalea’s facial features may have been further altered, other than the rhinoplasty, which ‘straightened and narrowed her nose’. He believes she may have opted for a chin augmentation and mandibular angle enhancement to achieve a more defined and sculpted jawline.

In a 2015 interview with Vogue, Azalea confessed to having had a breast enlargement. She has repeatedly denied rumors of butt implants, stating that her butt is real. After Azalea’s pregnancy in 2020, there were rumors about her postpartum body. Despite denying any assistance, there was still curiosity surrounding Azalea’s rapid return to her recognizable hourglass figure.

Overall, Azalea’s appearance has undergone significant changes, with her figure becoming more voluptuous and her facial features becoming more defined and sculpted. Despite these changes, she remains a prominent figure in the music industry, attracting a devoted following of fans with her infectious beats and bold lyrics.

Despite the denial, there was still curiosity surrounding Azalea’s rapid return to her recognizable hourglass figure. Some speculated that she may have undergone additional cosmetic procedures, while others believed that her body transformation was due to her rigorous workout routine and diet.

However, it’s worth noting that while Azalea’s physical appearance has certainly undergone significant changes over the years, her talent as a musician has remained a constant. She continues to release hit singles and collaborate with other artists, earning critical acclaim for her work.

In fact, Azalea has also been recognized for her business acumen, having successfully launched her own makeup line and even created a presence for herself on the subscription-based adult entertainment platform OnlyFans. With her loyal fan base and entrepreneurial spirit, it’s clear that Iggy Azalea is much more than just her appearance.

In conclusion, Iggy Azalea’s transformation has been a subject of fascination for many fans and critics alike. While her changing appearance has been well-documented, her success in the music industry and her entrepreneurial ventures speak to her talent and business acumen. Ultimately, Azalea’s story serves as a reminder that one’s appearance should not overshadow their accomplishments and talents.

Iggy Azalea Before And After Plastic Surgery Transformation & What Kind Of Surgery She Got?

In a recent interview, Iggy Azalea said that the rumors that she had plastic surgery to get back in shape after giving birth were untrue.

The 30-year-old Australian rapper credited a balanced diet and the fact that she was in terrific shape before becoming pregnant for her toned body, which she revealed to a fan on Twitter.

While that may be true, it doesn’t rule out the possibility that the Fancy hitmaker had had surgery in the past.
From a rumored chin implant to a nose operation and breast augmentation, Iggy’s look has undergone a dramatic transformation over the years.

Recent photographs of the celebrity reveal a very different person from the young blonde who burst into the scene in 2012.

Iggy looks very different in photos from when she was 23 years old. She has smaller lips, a bigger nose, and a flatter breast.

She has been quite forthright about her plastic surgery history, which includes a rhinoplasty and breast implants.

Iggy Azalea Before And After

But she insists her naturally large buttocks aren’t anything to be ashamed of.

Dr. Randal Haworth of Beverly Hills, who examined the singer last year, speculated to Daily Mail Australia that she may have had more cosmetic surgery to alter the structure of her face.

Although Dr. Haworth has not personally seen or treated Iggy, he notes that she has made some “subtle” and “wonderful” improvements.

Read More:

Iggy, in his opinion, is a great “canvas” for a plastic surgeon to show off his or her skills.

Results can be magnificent and undetectable to the untrained eye if done correctly.

Dr. Haworth speculates that Iggy may have had “a chin augmentation as well as mandibular angle enhancement to give her a more refined, “modelesque” jawline” in addition to her rhinoplasty, which he says “straightened and narrowed her nose.”
She could have had this done with solid silicone implants or with commercially available injectable fillers, but in either case the results would be “spectacularly non-obvious,” as he put it.

Iggy, who was born in Mullumbimby, NSW, and who came to the United States when she was 16 years old, has always been open about the fact that she had breast implants implanted.

“I acquired larger boobs four months ago!” She revealed her lifelong preoccupation with the idea to the fashion bible Vogue in 2015.

She addressed her decision to go public with her new appearance in an interview with E! afterward.

‘I love them so much I had to talk about them,’ she said. ‘ Everyone agreed that “I don’t believe you need to say anything since no one would ever know because they’re so little”. Rather than keeping my thoughts to myself, I blurted out, “I know but I’m just going to say it [because] I’m a blabber mouth!”

I think it would be better if I didn’t have a secret. It’s easier to say it out loud, she said, since you don’t have to fear that someone would go looking for it.

Read More:

The rumors that bootylicious Iggy has had “butt implants” persist, despite her openness about her willingness to undergo surgical procedures.

She denied having bum implants in an interview with Australian radio hosts Stav, Abby & Matt in 2017. Although they aren’t my natural breasts, this is my actual butt.
Iggy’s incredible post-baby physique is the result of strict dieting and intense exercise, she said earlier this week, ruling out plastic surgery as a possible explanation.

On Monday, a Twitter user commented on her looks by writing, “I’m not having a baby till I can afford what these celebs are doing to look like weeks after giving birth.”

In response, Iggy tweeted, “All you have to do is monitor what you eat when you’re pregnant and already have a six pack previously. It’s risk-free; all you need is the willpower to see it through for nine months.

Iggy Azalea’s cosmetic surgery transformation revealed amidst blackfishing allegations

Iggy Azalea has been quashing rumors that her looks are courtesy of various surgical procedures just like she denied blackfishing recently

Iggy Azalea was in the news recently after fans and critics leveled “blackfishing” allegations against the rapper. In layman terms, blackfishing is similar to catfishing and it refers to someone who resorts to different ways – including makeup – to appear Black or racially ambiguous. The term was coined by hip-hop journalist Wanna Thompson in 2018. 

The Australian-born rapper said she shot the video of ‘I Am The Stripclub‘ in a dimly lit room with red lights. Rubbishing all blackfishing allegations, Azalea said she has been using the same makeup for years and has been the same color as she has always been. It’s the same makeup from every other part of the video just with a Smokey eye and different wig. Just ignore them, who cares? Let ’em talk,” she said while replying to one of her fans on Twitter.

This is not the first time Azalea’s looks have sparked controversy. She has been battling plastic surgery rumors for many years. Even though she has admitted to having gotten rhinoplasty and breast augmentation, Azalea in the past claimed her famous butt is courtesy of a clean diet and exercise while continuing to never address rumors about her silicone jaw amongst other things. Here’s a rundown of all the times Azalea defended herself over her transformed looks.

READ MORE

Rapper Bhad Bhabie claps back at ‘blackfishing’ accusations, says people should worry about coronavirus instead

What is Jesy Nelson’s ethnicity? Ex-Little Mix star accused of ‘blackfishing’, fans claim Ariana Grande does it

‘It is my real butt’

In 2017, Azalea in an interview with Stav, Abby, and Matt on an Australian radio program said, “No, I don’t have bum implants! They’re not my real boobs, but it is my real butt.” After having a baby, Iggy debuted her washboard abs in a couple of months and once again denied rumors that she went under the knife to look perfect. Azalea is very connected to her fans on Twitter and communicates with them throughout the day. It was during one such interaction where she said she was in great shape when pregnant and that coupled with a healthy diet was responsible for her godly post-pregnancy body. 

However, Azalea has never shied away from talking about her boobs which she got done in 2015, candidly at that. “Four months ago, I got bigger boobs! I’d thought about it my entire life,” she told Vogue the same year. Talking to E! about why she chose to address it in the media, she said, “I love them so much I had to talk about them,” she revealed. “Everybody did say, ‘I don’t think you need to say it because no one will ever know because they’re so small.’ I said, ‘I know but I’m just going to say it [because] I’m a blabbermouth!”‘ Azalea added before saying, “I’d feel better not to have some secret. It’s much freer to say it and then you don’t have to worry someone will dig it up,’ she added.”

Iggy Azalea performs onstage during iHeartRadio Jingle Ball 2014, hosted by Z100 New York and presented by Goldfish Puffs at Madison Square Garden on December 12, 2014 in New York City. (Photo by Mike Coppola/Getty Images for iHeartMedia)

Dr Randal Haworth, a Beverly Hills plastic surgeon, spoke to a publication in 2019 and noted that the musician might have made additional changes to her face more than she lets on. Azalea had been open about getting a rhinoplasty and breast augmentation but Haworth argued that she might have invested in a couple of “subtle” and “beautiful” procedures to fine-tune her already flawless visage. “Iggy is what I would describe as an excellent ‘canvas’ on which a plastic surgeon can reveal his work,” Haworth observed. “When done right, results can be sublime and indiscernible to a layman’s eye,” he said.

Haworth himself didn’t treat Azalea but he believed she underwent “a chin augmentation as well as mandibular angle enhancement to give her a more refined, modelesque jawline.” He further added, “This can be done either with solid silicone implants or off-the-shelf injectable fillers, but either way, her results are spectacularly non-obvious.”

Azalea hasn’t commented on Haworth’s observations about her looks.

If you have a news scoop or an interesting story for us, please reach out at (323) 421-7514

My, how you’ve changed! Alex Perry looks worlds away from his days as a budding designer – as he sports a VERY puffy face at Fashion Week

Alex Perry has been in the fashion game for over two decades, winning global praise for his eponymous couture label. 

And just as fashion trends change over the years, so too has the 58-year-old’s facial features.  

Stepping out at Afterpay Fashion Week Australia on Wednesday to host a live interview with P.E Nation designers Pip Edwards and Claire Tregoning, the catwalk king looked worlds away his days as fashion newcomer.  

Alex, who has made no secret of his love of fillers and Botox, sported a distinctly puffy visage as he chatted to the women on-stage. 

His lips and cheekbones appeared to jut out more than they did in his youth, while his complexion seemed very taut. 

It comes after a leading plastic surgeon accused the Australian fashion designer of ‘excessive’ use of anti-wrinkle injections.

Speaking to Daily Mail Australia in 2018, Beverly Hills surgeon to the stars Dr. Randal Haworth observed how Alex, 55, looks remarkably different in before and after photos and may have taken things too far. 

Dr Haworth claimed Alex’s face now looked ‘crowded’ as a result of ‘too much’ filler.

‘There is no denying that Mr. Perry has undergone significant change to his countenance,’ Dr. Haworth noted.

‘Compared to his younger self, his face is now ‘crowded’, making his eyes appear smaller and closer set.

‘Most likely, a generous recipe of injected filler and more than a drizzle of Botox in and around his forehead, brows and temples contributed to this look.’

‘Additionally, his mid-face (the area between his lower eyes and upper lip) has been amply plumped to attain the ‘apple cheek’, a feature I feel is best left flatter in men,’ Dr. Haworth added.

The doctor went on to say that it’s hard to determine whether Alex’s cosmetic work is permanent or temporary.

‘Hopefully the fillers used to obtain Mr. Perry’s current look are absorbable and therefore temporary,’ he said. 

‘However, if fat was used (which is a permanent, living filler) his options, unfortunately, will be more limited.’

Unsure: The doctor went on to say that it’s hard to determine whether Alex’s cosmetic work is permanent or temporary

Alex, whose celebrity fans include Rihanna and Kim Kardashian, told Yahoo in 2013 that he is not ashamed of using fillers and Botox. 

‘There is nothing not real, there are a few fillers and there is a bit of Botox but that’s that. That’s normal, right?… It’s all real. It’s all real,’ he said.     

In 2016, the Australia’s Next Top Model judge was famously criticised for his appearance by one of the show’s contestants, Kassidy Ure.

After Alex criticised her photos, the then 21-year-old sniped back: ‘At least my lips are real!’ 

Open book: Alex, whose celebrity fans include Rihanna and Kim Kardashian, told Yahoo in 2013 that he is not ashamed of using fillers and Botox

Convicted drug smuggler Schapelle Corby looks almost unrecognisable as she unveils her glamorous reality TV transformation ahead of SAS Australia

Schapelle Corby is on the campaign trail promoting Channel Seven’s military-style reality show SAS Australia.

But viewers would be forgiven for not recognising the convicted drug smuggler as she did the breakfast TV rounds on Monday.

The 43-year-old looked very different compared to her days locked up in Bali’s Kerobokan Prison as she was interviewed on Sunrise shortly before 8am.

Her eyebrows appeared noticeably fluffier than they were in the early 2000s, while her hair was more voluminous thanks to a set of perfectly curled extensions. 

Schapelle, who has denied rumours of cosmetic work such as Botox and fillers, also showed off her age-defying complexion, smooth forehead and plump lips.

The former drug mule later appeared on The Morning Show, wearing a striking red frock that offered a glimpse of her cleavage.

The interview also highlighted the impressive length of Schapelle’s hair extensions, which tumble well past her shoulders.

Beverly Hills surgeon Dr. Randal Haworth previously told Daily Mail Australia that Schapelle may have invested in ‘non-invasive work’ to achieve her youthful looks.

‘It is not hard to imagine that a stint in an Indonesian prison would be a less than welcome holiday, so it is understandable that anyone would want a fresh start after that,’ he said in June 2018. ‘It seems as if Ms Corby is no exception to that rule.’

Dr. Haworth was of the opinion Schapelle had ‘undergone subtle facial rejuvenation’.

‘I don’t believe she underwent any plastic surgery per se,’ he claimed. ‘But she most likely had non-invasive work to achieve her current look.’

Jailed: Schapelle served her sentence at Kerobokan Prison, alongside several other Australian drug criminals including members of the Bali Nine. Pictured at Denpasar District Court in 2005


Ellen DeGeneres on plastic surgery spree after aging quickly amid criticisms: Rumor

Ellen DeGeneres recently made a public appearance when she hung out with Kevin Hart. Photos of the comedian show that she looks a bit older.

But Globe wanted to create an entire storyline about Ellen DeGeneres aging extensively amid the recent criticisms she has received. They even published an old photo of the funny woman in this week’s issue.

Ellen DeGeneres criticisms have left a lasting impact on her face

A source claimed that the recent allegations against DeGeneres and Ellen Show had left an ugly impact on the host.

“It shows in the bags under her eyes, the saggy cheeks, and jaw. She’s breaking out something terrible, and her skin looks blotchy from all the stress she’s been under. Even with makeup on, she looks haggard,” the source said.

Ellen DeGeneres panicking over a recent change in appearance

The insider also claimed that DeGeneres has always been conscious of her image. As such, she couldn’t take the recent changes in her appearances. And she has, allegedly, booked appointments with experts.

“She’s booking appointments with dermatologists and surgeons, demanding Botox fillers, a facelift and eye-lift, surgery to tighten her neck, and microdermabrasion. She doesn’t care what it costs because money is no object,” the source said.

Ellen, Portia alleged marital problems

Ellen DeGeneres is also, allegedly, struggling with her marriage to Portia de Rossi. And their issues have also, allegedly, contributed to her aging appearance.

“They’ve had their share of problems, and Ellen’s diva behavior is to blame. That’s exactly what’s gotten Ellen into so much trouble with her staffers, past, and present,” the source said.

But even though DeGeneres and de Rossi are, allegedly, having marital issues, the latter still supports her wife’s desire to look younger.

“Portia’s supporting Ellen’s surgery plans, too. Anything to make Ellen feel better,” the source said.

‘Ellen Show’ host’s face costs $1 million?

Rumors about DeGeneres getting plastic surgery have been rife for months. And the recent claims weren’t the only ones made by Globe.

Two years ago, the tabloid claimed that the Ellen Show host’s entire face has gone under the knife. And all of the procedures combined, allegedly, cost DeGeneres $1 million.

“It’s quite obvious she underwent a full face-life – and everything else, as well. She had almost everything was done that can be done – and I suspect a nose job too,” New York-based plastic surgeon Dr. Yoel S. Shahar said.

Meanwhile, Dr. Randal Haworth also said that DeGeneres’ ears also show signs of a facelift.

A source also said that over time, Ellen DeGeneres, allegedly, coughed up a million to fix her entire face. However, one should take the claims made by the tabloid with a grain of salt.

Page 1 of 8
1 2 3 8